Best Cardiac Catheterization in Saki Naka at Henotic Diagnostics
Accredited by National Bodies
Best Cardiac Catheterization in Saki Naka
Accurate, fast, and reliable diagnostic services near you in Saki Naka, Central Suburbs. Experience state-of-the-art technology with same-day reporting.
About Cardiac Catheterization
Cardiac Catheterization | Heart & Coronary Diagnostic Care
Additionally, radial / Femoral Route: Micro-catheter inserted via wrist (transradial) or groin under live fluoroscopic guidance with minimal recovery downtime.
Dual Capability
Consequently, diagnosis & Stenting: Visualizes arterial stenosis with immediate capability for balloon angioplasty and drug-eluting stent (DES) deployment.
Furthermore, Direct Hemodynamics Telemetry
Moreover, chamber Pressures: Directly records intracardiac chamber pressures, cardiac output, and oxygen gradients to evaluate complex valve disease.
Therefore, select any chapter below to navigate directly to detailed clinical protocols, procedure explanations, preparation guidelines, diagnostic comparisons, accreditations, specialist consultations, and related diagnostic services.
Dossier Reading Completion:0 of 18 Chapters Read (0%)
Specifically, ~12 Min Total Read
Need Immediate Guidance or Cath Lab Scheduling?In particular, Direct patient concierge • Pre-catheterization workups across Navi Mumbai & Mumbai
In particular, Cardiac catheterization is a specialized medical procedure used to evaluate heart function, assess blood flow through the coronary arteries, and measure pressures inside the heart. For example, it helps cardiologists investigate certain cardiovascular conditions and determine appropriate treatment options.
As a result, at Henotic Diagnostics, patient education about cardiac catheterization focuses on understanding the procedure, its clinical purpose, preparation requirements, potential risks, and recovery considerations. In addition, the decision to perform this procedure should be based on an individual’s symptoms, medical history, diagnostic findings, and the treating cardiologist’s recommendations.
Consequently, MD Internal Medicine • Gold Medalist
Moreover, FSCAI (USA) • International Fellow
Therefore, CSI Life Member • India
In Particular, MMC Reg. No: 2008/04/1294 (Verified)
Kharghar Center OPD • 24/7 STAT On-Call
In Addition, Board Certified Cardiologist
AHA & ACC Guidelines Aligned
15+ Years Clinical Experience
Accordingly, Dr. Siddharth Sonkamble is an experienced Interventional Cardiologist specializing in complex coronary angiography, intracardiac pressure dynamics, and catheter-based cardiovascular therapeutics. Similarly, he oversees the clinical accuracy and patient safety protocols published by Henotic Diagnostics.
”Notably, Cardiac catheterization remains the gold standard when non-invasive findings require definitive anatomic visualization or when therapeutic coronary stenting is anticipated. In addition, ensuring patients understand procedural safety and individualized care is central to evidence-based cardiology.”
In contrast, all clinical indications and catheterization thresholds follow Class I & IIa consensus guidelines established by the American College of Cardiology.
Furthermore, AERB Low-Dose Radiation Survey
Ultimately, fluoroscopy equipment operates under valid AERB radiation registrations with real-time Dose Area Product (DAP) tracking to safeguard patient tissue.
Additionally, ISO 13485 & NABH Single-Use Mandate
Overall, zero reuse policy: 100% of vascular sheaths, micro-puncture needles, and pre-formed diagnostic catheters are individually barcode-tracked and single-use.
Specifically, Interventional Cardiology Masteries
Moreover, Specifically, Dr. Siddharth Sonkamble • Cardiac Catheterization Competencies & Case Volume
Furthermore, 15+ Years Active Practice
Consequently, Interventional Cardiology Practice Areas & Clinical Focus
Specifically, Advanced Coronary Interventions: Specializing in high-complexity coronary cases, multivessel disease, and emergency primary angioplasties across leading Mumbai and Navi Mumbai tertiary heart hospitals.
4,500+Coronary Angiographies
Meanwhile, extensive experience with >89% performed via transradial (wrist) access with same-day ambulation.
<55 minDoor-to-Balloon Primary PCI
Subsequently, rapid emergency revascularization for acute STEMI heart attacks well below the international 90-minute benchmark.
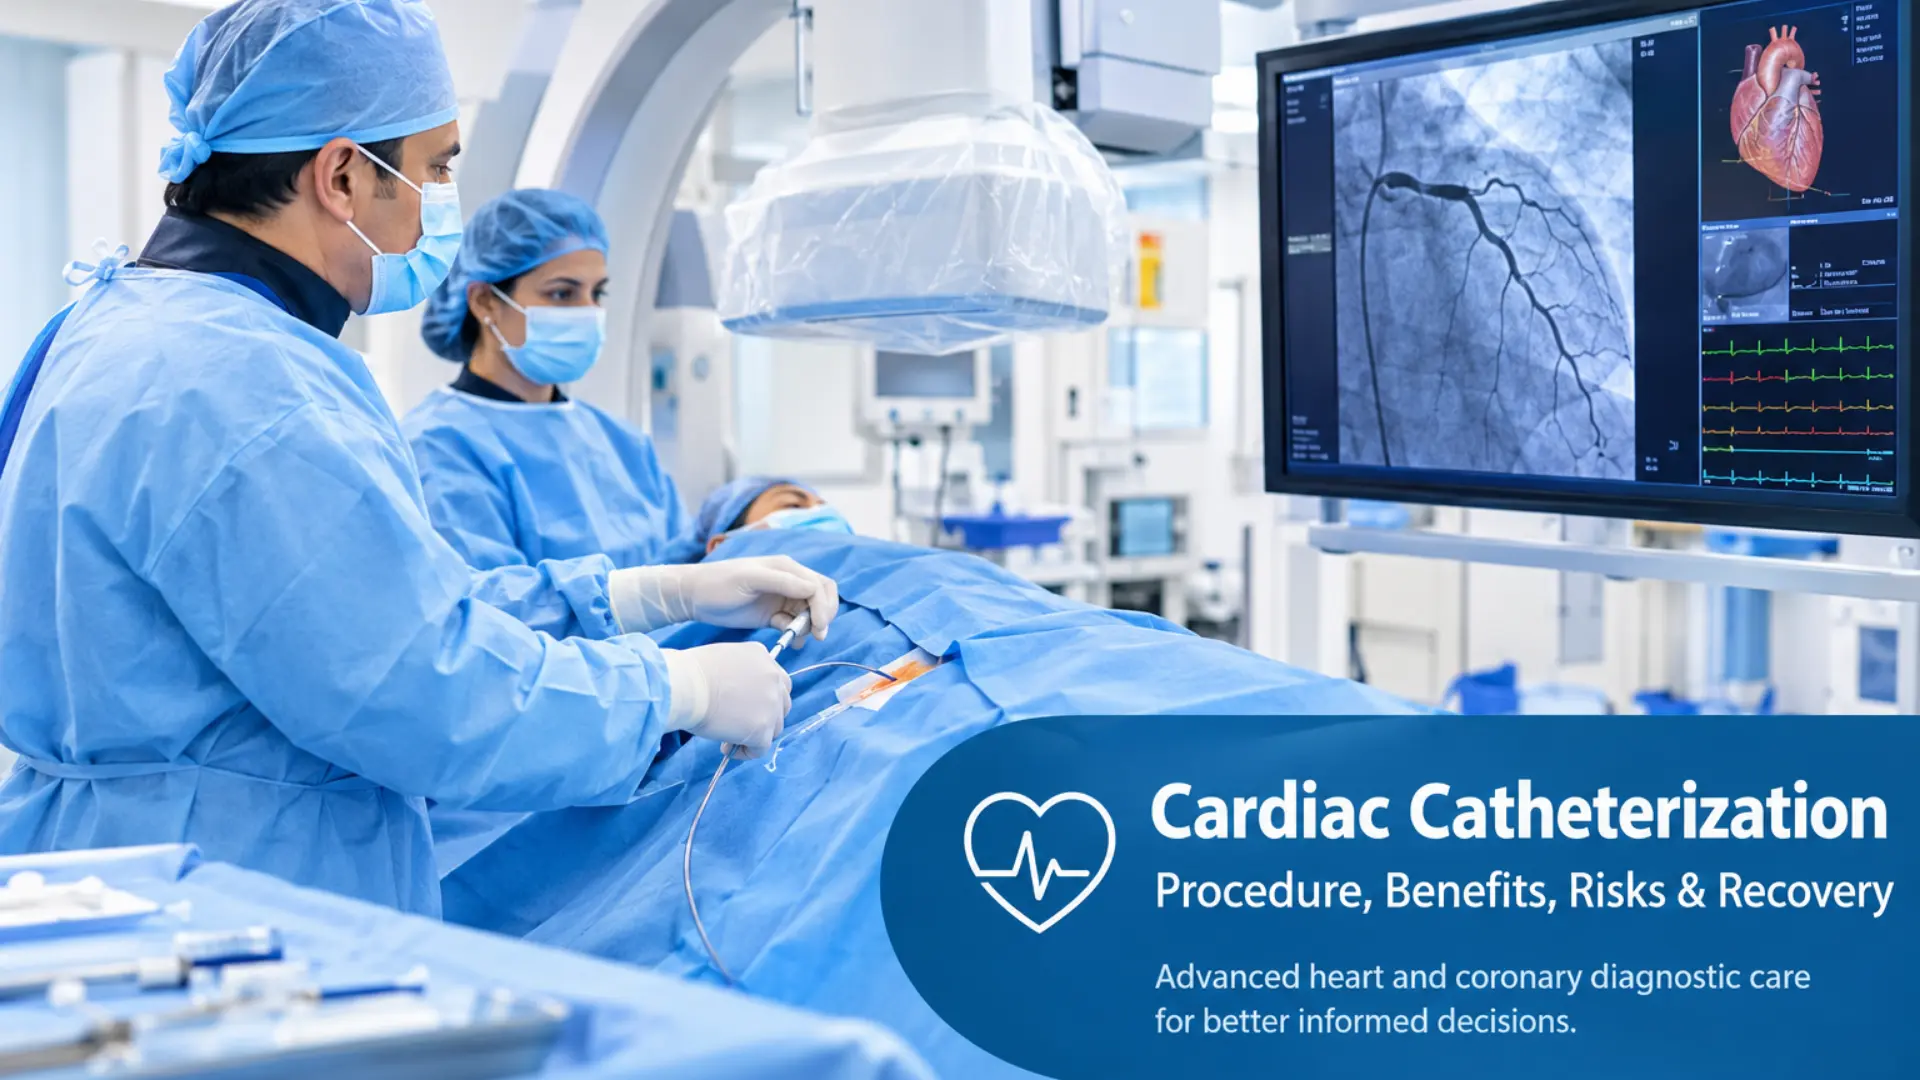
Notably, Cardiac catheterization is a minimally invasive procedure in which a healthcare professional guides a thin, flexible tube called a catheter through a blood vessel toward the heart. Accordingly, the catheter is commonly introduced through an artery or vein in the wrist or groin, depending on the purpose of the examination.
Similarly, during the procedure, clinicians may use X-ray imaging, contrast material, and specialized instruments to examine cardiovascular structures or obtain important physiological measurements.
In contrast, Cardiac catheterization can help evaluate coronary artery narrowing, certain heart valve conditions, congenital heart abnormalities, and abnormal pressures within the heart or pulmonary circulation. Ultimately, its exact role depends on the clinical indication.
Unlike a routine external examination, cardiac catheterization allows selected measurements and images to be obtained directly from within the cardiovascular system.
Anatomical Approach
Therefore, Vascular Access Routes for Cardiac Catheterization: Transradial vs. Transfemoral
Overall, clinical decision metrics governing the vascular pathway selected for catheter advancement.
Therefore, Arterial Caliber (Lumen Width)2.2 – 2.8 mm
Specifically, micro-puncture 20G/21G needle with 5-Fr / 6-Fr slender sheath
In addition, Bleeding / Hematoma Incidence< 0.1% (Near Zero)
Notably, Superficial wrist bone bed allows complete immediate mechanical compression
Similarly, Post-Cath Bed Rest Requirement0 Hours (Immediate Sitting)
Ultimately, Patient sits upright immediately; walks to recovery lounge in < 2 hours
In particular, Cardiac Catheterization Clinical Glossary & Jargon Decoder
Meanwhile, essential catheterization terms, hemodynamic metrics, and medical acronyms translated into plain clinical language.
Subsequently, Patient Education Standard
Specifically, showing all 6 clinical terms
Specifically: Coronary Stenosis
/Meanwhile, stuh-NOH-sis/ • Pathology
Subsequently, narrowing or constriction of a coronary arterial lumen caused by progressive atheromatous plaque buildup, restricting oxygen delivery to the heart muscle.
Furthermore: Drug-Eluting Stent (DES)
/Subsequently, stent/ • Therapeutic Device
Indeed, an expandable microscopic cobalt-chromium mesh scaffold coated with a time-released antiproliferative medication that permanently prevents scar tissue re-narrowing.
Additionally: Fractional Flow Reserve (FFR)
/Indeed, ef-ef-ahr/ • Hemodynamic Metric
With this in mind, a precision pressure-wire measurement calculated across a blockage. To clarify, an FFR value ≤ 0.80 confirms blood flow starvation and indicates stenting benefit.
Consequently: Pneumatic TR-Band
/Clearly, t-r-band/ • Hemostasis Device
A transparent wrist compression cuff inflated with titrated air to secure complete radial artery hemostasis while maintaining continuous ulnar collateral circulation.
Moreover: Iso-Osmolar Non-Ionic Contrast
/Specifically, KAHN-trast/ • Imaging Agent
In fact, a low-risk radiopaque fluid formulated to match normal human serum osmolarity (~290 mOsm/kg), highlighting arteries in 4K X-ray without stressing kidney nephrons.
Therefore: Left Ventricular End-Diastolic Pressure
/Furthermore, LVEDP/ • Pressure Measurement
Specifically, direct catheter recording of intraventricular pressure at end-diastole, serving as a primary clinical marker for left heart compliance and heart failure staging.
Moreover, Why Is Cardiac Catheterization Performed?
Furthermore, a cardiologist may recommend cardiac catheterization when additional information is needed to diagnose a cardiovascular condition, assess its severity, or guide treatment.
In addition, Suspected Coronary Artery Disease & Cardiac Catheterization
Specifically, this procedure examines the coronary arteries when clinically indicated for critical narrowing or arterial obstructions.
Notably, Chest Pain Evaluation Through Cardiac Catheterization
Furthermore, interventional cardiologists investigate selected cases of unexplained or worsening suspected cardiac-related chest discomfort.
Similarly, Abnormal Cardiac Test Results Requiring Cardiac Catheterization
Additionally, this gold-standard study clarifies inconclusive or high-risk findings identified on stress testing, ECG, or echocardiography.
Ultimately, Heart Valve Assessment via Cardiac Catheterization
Moreover, hemodynamic catheterization accurately evaluates selected valve-related conditions and their physiological effects on intracardiac blood flow.
Overall, Heart Failure Evaluation via Cardiac Catheterization
Consequently, clinicians measure intracardiac pressures and investigate underlying myocardial causes in appropriate heart failure patients.
Additionally, during catheterization, the cardiologist measures the exact percentage of arterial lumen narrowing to determine whether medication, stenting, or bypass is indicated:
Consequently, minimal resistance to resting or exertional coronary blood flow. Moreover, myocardial oxygen demand is fully met during strenuous exercise.
Clinical Presentation:
Therefore, specifically asymptomatic. Often detected incidentally during coronary CT angiography or routine executive screening.
Recommended Treatment:
In particular, guideline-Directed Medical Therapy (GDMT): High-intensity statin therapy (Atorvastatin/Rosuvastatin), lifestyle optimization, strict blood pressure control. For example, stenting is NOT indicated.
Therefore, Lumen Narrowing: ~60%Moreover, Distal Perfusion: Borderline on Peak Exertion
Hemodynamic Impact:
As a result, visual estimation alone is insufficient. In addition, lesion may or may not cause true physiological ischemia during hyperemia.
Clinical Presentation:
Notably, occasional exertional breathlessness or atypical angina during intense stair climbing or brisk walking.
Recommended Treatment:
Accordingly, pressure-Wire Guided Assessment: If FFR ≤ 0.80 or iFR ≤ 0.89, proceed to Drug-Eluting Stent (DES). Similarly, if FFR > 0.80, continue medical therapy safely without stenting.
In contrast, significant translesional pressure drop. Ultimately, marked impairment of myocardial blood flow reserve leading to downstream myocardial hypoxia.
Clinical Presentation:
Overall, predictable exertional angina (retrosternal heaviness), positive treadmill test (TMT >2mm ST depression), resting ECG changes.
Recommended Treatment:
Meanwhile, percutaneous Coronary Intervention (PCI): Ad-hoc balloon angioplasty and Drug-Eluting Stent (DES) deployment in the same sitting. Subsequently, if left main or complex multi-vessel disease, evaluate for CABG.
Total Occlusion (100%)
Ultimately, Acute STEMI or Chronic Total Occlusion
In Addition, Lumen Narrowing: 100% (Complete Cutoff)Similarly, Distal Perfusion: Zero Direct Perfusion
Hemodynamic Impact:
Indeed, complete cessation of blood delivery through the primary lumen. With this in mind, myocardial viability depends entirely on retrograde collateral vessels.
Clinical Presentation:
To clarify, acute: Severe crushing chest pain, diaphoresis, acute myocardial infarction (heart attack). In fact, chronic: Refractory angina, ischemic cardiomyopathy.
Recommended Treatment:
Specifically, emergency Primary PCI: Urgent catheterization within <90 minutes door-to-balloon time to reopen the culprit vessel, aspirate thrombus, and restore TIMI-3 perfusion.
Furthermore, note: Not every patient with chest pain or an abnormal cardiac test requires catheterization. Non-invasive investigations and the overall clinical picture help determine the most appropriate next step.
Additionally, Cardiac catheterization encompasses several procedures. Consequently, the technique selected depends on the suspected condition and the information required.
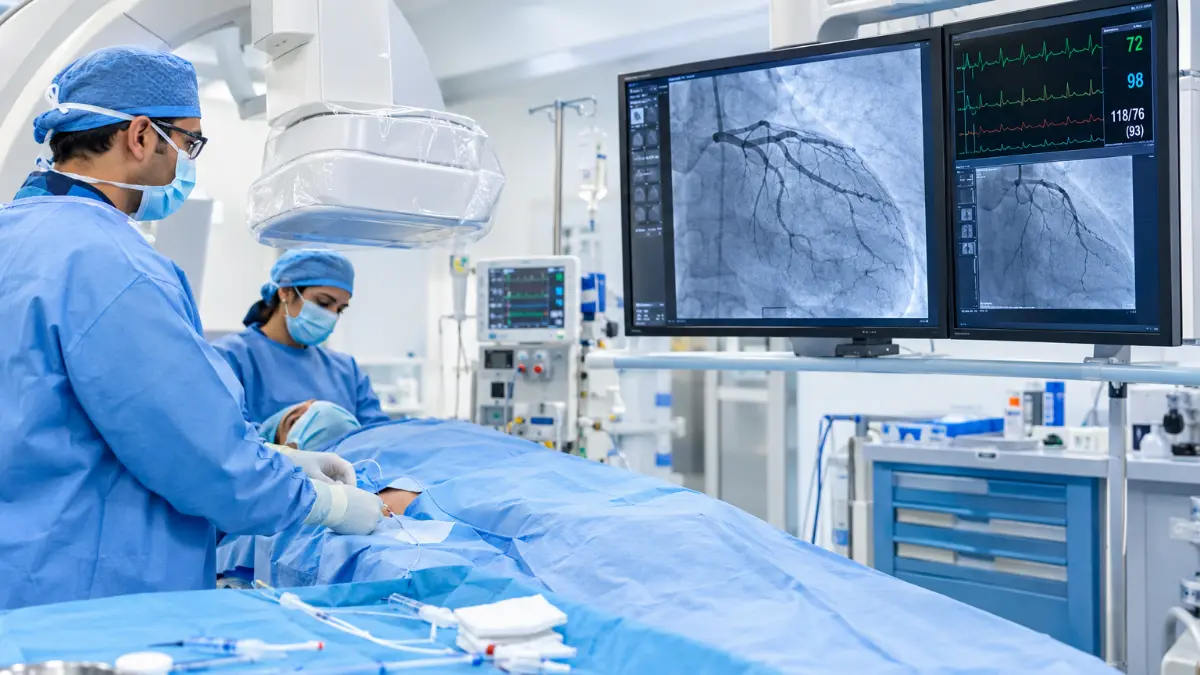
Similarly, Figure 1: High-Definition Coronary Angiography in Progress.
Ultimately, Real-time fluoroscopic cineangiography capturing radiopaque contrast media through the coronary arterial tree to pinpoint arterial narrowing, plaque burden, and myocardial perfusion dynamics.
Diagnostic Imaging
Generally, 1. Coronary Angiography
Moreover, Coronary angiography uses contrast material and X-ray imaging to visualize the coronary arteries. Therefore, it helps clinicians identify the location and extent of narrowing or blockage that may affect blood supply to the heart muscle. In particular, the findings assist cardiologists in evaluating medical management, angioplasty, stenting, or bypass surgery.
For example, right heart catheterization measures pressures in the right atrium, right ventricle, and pulmonary artery. It also evaluates cardiac output and haemodynamic parameters when assessing pulmonary hypertension, unexplained breathlessness, or complex heart failure.
Vascular RouteMeanwhile, Jugular / Arm / Femoral Vein
As a result, left heart catheterization provides access to selected measurements within the left side of the heart. In addition, depending on the approach and clinical purpose, it helps evaluate left ventricular pressure, aortic pressure, or other aspects of cardiac function.
Accordingly, 4. Cardiac Catheterization With Coronary Intervention
Notably, in certain cases, diagnostic catheterization is followed by a therapeutic procedure. Accordingly, percutaneous coronary intervention (PCI) may involve balloon angioplasty and placement of a coronary stent to improve blood flow through a narrowed artery during the same session or scheduled separately.
Specifically, Intravascular Pressure Waveform Architecture in Cardiac Catheterization
Similarly, select a cardiovascular circuit below to review selective catheter engagement, baseline intracardiac pressure telemetry, and clinical diagnostic value.
Furthermore, Anatomical Target: Left Main OstiumArterial Circuit
Overall, Left Anterior Descending (LAD) & Circumflex (LCx) Arteries
In contrast, supplies over 65% of left ventricular myocardial blood mass (“The Widowmaker” territory). Ultimately, selective cannulation assesses epicardial stenoses, bifurcation lesions, and distal runoff.
Specialized Dedicated CatheterSpecifically, Judkins Left (JL 3.5 / JL 4.0) • Extra Backup (EBU 3.5)
Furthermore, Consequently, Normal Luminal DiameterLMCA: 4.0–5.5 mm • Proximal LAD: 3.0–4.0 mm
Consequently, Anatomical Target: Right Coronary OstiumArterial Circuit
Meanwhile, Right Coronary Artery (RCA) & Posterior Descending Artery (PDA)
Overall, courses in the right atrioventricular groove to supply the right atrium, right ventricle, sinus/AV nodes, and inferior diaphragmatic left ventricular wall in 85% of right-dominant hearts.
Moreover, Dedicated CatheterFurthermore, Judkins Right (JR 4.0) • Amplatz Right (AR-1 / AR-2)
Therefore, Similarly, Normal Luminal DiameterProximal RCA: 3.5–4.5 mm • Distal PDA: 2.0–2.8 mm
Conduction System Alert: Right coronary cannulation requires continuous bradycardia and AV node monitoring due to SA nodal branch proximity.
Therefore, Anatomical Target: Left Ventricle CavityVentricular Chamber
Subsequently, Left Ventriculography & End-Diastolic Pressure (LVEDP)
Meanwhile, the catheter traverses the aortic valve into the LV chamber. Subsequently, measures real-time intraventricular pressures and calculates global Ejection Fraction (LVEF %) via high-flow power injection.
Notably, Dedicated CatheterAdditionally, Pigtail Catheter (5-Fr / 6-Fr with multiple side holes)
In particular, Real-Time Cath Lab Waveform Telemetry25 mm/s
LV SYS / LVEDP126 / 10
mmHg
Furthermore, CALCULATED EF62%
Normal
Additionally, AO GRADIENT2
mmHg
Consequently, LVEDP Clinical Threshold: LVEDP > 18 mmHg confirms elevated left ventricular filling pressure consistent with diastolic heart failure.
In addition, Anatomical Target: Pulmonary CirculationVenous & Pulmonary
Specifically, Right Heart Catheterization (Swan-Ganz Thermodilution)
Indeed, introduced via internal jugular or femoral vein into the pulmonary bed. With this in mind, obtains gold-standard hemodynamic pressures and measures thermodilution Cardiac Output to classify pulmonary hypertension.
Similarly, Wedge Pressure Gold Standard: PCWP ≤ 15 mmHg with mean PA pressure > 20 mmHg definitively establishes Pulmonary Arterial Hypertension (Pre-Capillary).
Additionally, Same-Session Therapeutic Capability
Furthermore, From Diagnostic Cardiac Catheterization to Immediate Stenting: Ad-Hoc PCI
When an angiogram detects a critical stenosis (>70% arterial blockage), treatment can be performed immediately in the same 45-minute session without a second puncture or separate hospital stay.
Specifically, Stage 1 Intake • 00–20m
Clearly, Diagnostic Cineangiography
To clarify, radiopaque dye reveals the exact coronary anatomy, bifurcations, and pinpoint location of the narrowed vessel segment.
Furthermore, Preparation 2 • 20–25m
Specifically, On-Table Assessment & Consent
In fact, the interventional cardiologist discusses lesion severity with the patient/family and initiates the pre-approved interventional protocol.
Additionally, Cinefluoroscopy 3 • 25–40m
Furthermore, Guidewire & Stent Deployment
Specifically, a 0.014-inch microwire crosses the stenosis. Furthermore, a balloon pre-dilates the lesion, followed by precise deployment of a Drug-Eluting Stent (DES).
Consequently, Band Hemostasis 4 • 40–50m
Finally, Flow Restoration & Closure
Additionally, final angiography confirms 100% TIMI-3 flow restoration. Consequently, the sheath is painlessly removed and a radial TR-Band compressor is applied.
Single Puncture: No second arterial access needed
Ultimately, Single Contrast Load: Protects kidney function
Overall, Rapid Discharge: Same-day or overnight observation only
Furthermore, 35–45 minClosure & Hemostasis
TR-Band • Post-Cath Bed
Diagnostic Engineering
Additionally, Inside the Cardiac Catheterization Lab: Advanced Procedural Architecture
In particular, a specialized, high-technology medical environment engineered for sub-millimeter precision, patient comfort, and continuous hemodynamic telemetry:
System 01
Moreover, Flat-Panel Digital C-Arm Fluoroscopy
For example, a robotic C-arm rotates around the radiolucent carbon-fiber procedural bed to capture compound angulations (LAO Cranial, RAO Caudal) without shifting the patient. Emits ultra-low pulsed X-rays while producing crystal-clear high-definition 1024×1024 digital cineangiograms.
Accordingly, direct integration with Fractional Flow Reserve (FFR/iFR) optical pressure wires and Intravascular Ultrasound (IVUS) to visualize atheromatous plaque morphology, calcium distribution, and stent wall apposition with microscopic clarity.
Similarly, explore the sub-millimeter diagnostic catheters, hydrophilic sheaths, and arterial closure devices utilized during cardiac catheterization.
Specifically, 5F / 6F Radial SheathPrimary Access
Notably, Hydrophilic-Coated Radial Sheath
In contrast, ultra-thin walled, low-friction polymer sheath designed for atraumatic radial cannulation. Ultimately, minimizes arterial spasm and post-procedure discomfort.
Clinical Role: Furthermore, initial micro-access into radial/femoral lumen
Additionally, Judkins Left (JL 3.5 / 4.0)Left Coronary System
Ultimately, Judkins Left Coronary Catheter
Pre-shaped curvature tailored to naturally seek and engage the Left Main Coronary Artery (LMCA) ostium from the ascending aorta.
Construction: Additionally, braided stainless-steel wire for 1:1 torque
Tip Safety: Consequently, soft, atraumatic non-tapered radiopaque tip
Primary Targets: Moreover, left Anterior Descending (LAD) & Circumflex (LCx)
Cine Views: Therefore, RAO Caudal, LAO Cranial, Spider views
Judkins Right & Universal RadialMeanwhile, RCA & Dual Engagement
Overall, Judkins Right (JR 4.0) & Tiger / Jacky Catheters
Meanwhile, specialized curves for right coronary artery cannulation and universal single-catheter radial solutions that image both arteries without catheter exchange.
Tiger / Jacky Tip: In particular, angled secondary bend for dual-coronary imaging
Torque Response: Notably, high rotational responsiveness with minimal friction
Patient Benefit: In addition, reduces procedure time and catheter exchange cycles
Safety Limit: Accordingly, continuous pressure monitoring to verify un-damped flow
0.035” PTFE J-Tip WireAortic Tracking
Meanwhile, Diagnostic Conduit Guidewire
Subsequently, flexible J-curved guidewire providing safe tracking through peripheral arterial branches up into the ascending aortic root.
Core Wire: Similarly, spring-coil stainless steel with PTFE coating
Tip Design: Ultimately, 1.5–3.0 mm atraumatic soft J-curve
Safety Feature: Overall, deflects away from vessel wall bifurcations
Clinical Role: Meanwhile, leads diagnostic catheters safely to the aorta
0.014” Nitinol Steerable WireCoronary Navigation
Subsequently, Micro-Coronary Steerable Guidewire
Indeed, ultra-thin nitinol wire with shaping ribbon used when physiological assessment (FFR/iFR) or therapeutic stenting is indicated.
Diameter: Subsequently, 0.014 inches (~0.36 mm)
Tip Visibility: With this in mind, gold or platinum radiopaque distal coils
Sensor Technology: Specifically, micro-piezoelectric pressure sensor for FFR
With this in mind, active closure systems (Angio-Seal, Perclose) delivering bio-absorbable collagen or surgical sutures directly to the femoral arteriotomy.
Deployment Time: In particular, immediate mechanical sealing (<2 minutes)
Ambulation: Notably, reduces bed rest from 6 hours to 2 hours
Bio-Absorption: Naturally resorbed by the body within 60–90 days
Clinical Benefit: In addition, drastically decreases groin hematoma rates
To clarify, the interventional cardiologist reviews patient symptoms, detailed medical history, previous ECG/echo investigations, baseline renal profiles, anticoagulant regimens, contrast allergies, and confirms informed procedural consent.
02
Subsequently, Sterile Preparation 2: Local Anesthesia & Site Draping for Cardiac Catheterization
Clearly, Local Infiltration • Pain-Free
In fact, the patient is comfortably positioned on the fluoroscopy table under multi-parameter vital telemetry. Specifically, after sterile surgical prep, a rapid-acting local anesthetic numbs the radial wrist or femoral access site; mild conscious sedation is administered if indicated.
Furthermore, a slender micro-puncture sheath (5F/6F) is gently placed into the artery. Additionally, under live low-dose X-ray fluoroscopic guidance, a specialized diagnostic catheter is smoothly advanced through arterial conduits to the coronary ostia without vessel discomfort.
Consequently, radiopaque contrast agent is selectively injected into the coronary tree from multiple synchronized C-arm angles. Real-time digital cineangiograms record arterial blockages while high-fidelity transducers capture intracardiac chamber pressures and oxygen saturation gradients.
Moreover, the cardiologist immediately reviews lesion severity and blood flow dynamics. Therefore, if a critical blockage is identified and indicated, the physician can seamlessly proceed with balloon angioplasty and precision drug-eluting stent (DES) implantation during the same procedure.
06
Finally, Hemostatic Closure 6: Sheath Removal & Band Placement After Catheterization
Ultimately, Targeted Hemostasis
In particular, the diagnostic catheter and sheath are carefully withdrawn. For example, hemostasis is achieved using an adjustable pneumatic compression band (radial TR-Band) or vascular closure device. As a result, the patient is transferred to step-down recovery for monitored vital observation.
In addition, proper clinical preparation significantly reduces procedural complications, ensures contrast safety, and allows the catheterization team to individualize vascular access and sedation strategies.
In contrast, verify essential intake items before departing for the Henotic Cath Lab suite.
0 of 5 Ready
Furthermore, Cardio-Pharmacology Directive
Therefore, Pre-Cardiac Catheterization Medication Management: Hold vs. Continue Protocol
Ultimately, certain daily medications interact with fluoroscopic contrast media or vascular access puncture sites. Overall, always confirm individual titration with your Henotic cardiologist:
Direct Oral Anticoagulants (DOACs): Apixaban, Rivaroxaban, Dabigatran are specifically withheld for 24–48 hours prior to reduce puncture hematoma risk, depending on renal function.
HOLD (3–5 Days)
Warfarin (Coumadin): Discontinued 3 to 5 days prior; INR verified on arrival (target INR <1.8 for femoral, <2.2 for transradial). Furthermore, low molecular weight heparin bridging is used if a mechanical valve is present.
CONTINUE
Aspirin & P2Y12 Inhibitors: Low-dose Aspirin (75–100mg) is generally continued unless specifically advised otherwise, especially in patients with prior coronary stents.
Metformin (Glucophage): Must be withheld morning of procedure and for 48 hours post-procedure. Consequently, resumed only after repeat serum creatinine confirms stable kidney function to prevent contrast-induced lactic acidosis.
HOLD (3 Days)
SGLT2 Inhibitors (Empagliflozin, Dapagliflozin): Withheld 3 days prior to reduce the risk of peri-procedural euglycemic diabetic ketoacidosis (euDKA) during fasting.
ADJUST DOSE
Insulin & Sulfonylureas (Glimepiride): Morning oral hypoglycemics held while fasting. Long-acting basal insulin specifically reduced to 50% dose on procedure morning. Therefore, capillary blood glucose is monitored bedside every 2 hours.
Beta-Blockers (Metoprolol, Bisoprolol, Carvedilol): Take on schedule morning of procedure with a tiny sip of water. Maintaining heart rate control (<70 bpm) improves fluoroscopic coronary visualization and hemodynamic stability.
MORNING HOLD
ACE Inhibitors & ARBs (Ramipril, Telmisartan, Losartan): Often held on the morning of catheterization to prevent sudden intra-procedural hypotension during sedation and reduce contrast nephrotoxicity risk.
CONTINUE
Lipid-Lowering Statins (Atorvastatin, Rosuvastatin): Continue as usual. Pre-procedural statin loading has proven plaque-stabilizing and cardioprotective benefits.
Furthermore, Omega-3 Fish Oil, Vitamin E, Ginkgo Biloba, Ginseng, Ibuprofen
HOLD (7 Days)
Herbal Antiplatelet Supplements: Ginkgo Biloba, Garlic extract capsules, Ginseng, high-dose Vitamin E, and St. John’s Wort possess antiplatelet activity and must be paused 7 days prior.
HOLD (48h)
NSAIDs (Ibuprofen, Naproxen, Diclofenac): Pause 48 hours before the procedure to protect renal filtration and prevent prostaglandin inhibition prior to contrast dye exposure. Meanwhile, Paracetamol (Acetaminophen) is safe if needed for mild pain.
CONSULT TEAM
Complete Prescription Strip Verification: Bring all original medication strips and bottles to the Cath Lab holding suite for on-table verification by the cardiology nursing supervisor.
In particular, Important Medication Warning for Cardiac Catheterization Patients
Meanwhile, never stop prescribed medication or change a dose without instructions from the treating clinician. Fasting requirements and medication adjustments vary by procedure and individual circumstances.
Subsequently, Cardiac catheterization is commonly performed using local anaesthesia at the insertion site. Indeed, patients may experience a brief sting when the anaesthetic is administered, along with pressure or mild discomfort during catheter insertion.
With this in mind, a fine micro-needle administers local anesthetic (Lignocaine) at the puncture site (wrist or groin). To clarify, patients feel a quick initial sting, followed by total local numbness within seconds.
Catheter TravelZero Arterial Pain
Notably, 2. Arterial Advancement
In fact, arteries lack interior pain nerve receptors. Specifically, once through the skin, catheter advancement through the vascular tree to the heart coronary ostia is painless; patients only perceive mild pressure.
Contrast InjectionWarm Flush (~20s)
Similarly, 3. Radiopaque Dye Flushing
Furthermore, as the radiopaque contrast agent is injected under fluoroscopy, a distinctive warm flush or mild metallic taste travels through the body. Additionally, this is completely normal and dissipates in 20–30 seconds.
Sedation CareConscious Relaxation
Ultimately, 4. Anxiolytic Conscious Sedation
If requested or indicated, mild intravenous sedation helps eliminate procedure anxiety while keeping the patient conscious, breathing independently, and able to respond to physician guidance.
Notably, Patient Sensory Reality Check
In addition, What You Actually Feel During Cardiac Catheterization: Sensation Map
Consequently, arteries have no sensory pain nerve endings. Moreover, here is exactly what you will experience from room entry to recovery:
Therefore, a pediatric-gauge micro-needle infiltrates a small amount of local anesthetic (Lignocaine 2%) at the wrist or groin crease. In particular, you will feel a brief sting similar to a mosquito bite or routine blood draw. For example, within seconds, the entire area becomes fully numb.
Zero general anesthesia needed Rapid 8-second onset Tested for total numbness before start
Perceived Sensation:Zero Arterial Pain
Meanwhile, Vascular Catheter Navigation
As a result, human arterial walls do not possess somatic pain sensory receptors. In addition, as the slender 2mm diagnostic catheter advances through the radial artery into the aorta and coronary ostia, you will feel absolutely no internal pain. Notably, most patients only feel faint tactile pressure at the wrist as the cardiologist adjusts direction.
Indeed, No internal nerve endings in blood vessels Continuous 12-lead ECG telemetry You can speak to your doctor anytime
Accordingly, when non-ionic contrast medium is injected to highlight coronary blockages under fluoroscopy, you may feel a warm, flushing sensation traveling down your chest, back, or pelvic region. Similarly, this is a normal physiological vascular response that peaks and resolves completely within 15–20 seconds.
Clearly, Iso-osmolar safe non-ionic contrast Transient and completely harmless Hydration flushes dye quickly via kidneys
Perceived Sensation:Overall, Firm Wrist Pressure (No Stitches)
Indeed, Hemostatic Closure & TR-Band
In contrast, once imaging or stenting is complete, the sheath is gently withdrawn. Ultimately, for radial procedures, an inflatable pneumatic wristband (TR-Band) is placed to provide precise, gentle pressure over the radial puncture. Overall, no surgical stitches or cuts are required. Meanwhile, the band is gradually deflated over 2–4 hours.
Specifically, Zero surgical skin sutures needed Immediate post-procedure walking permitted Precision air pressure prevents bruising
Meanwhile, Anesthesia & Sedation Protocol
Notably, Anesthesia and Sedation Spectrum for Cardiac Catheterization
Subsequently, ASA & ACC Patient Comfort Standard
Clearly, Cardiac Catheterization Anesthetic Options: Local vs. Conscious Sedation
Standard Transradial Practice: Subcutaneous 1% to 2% Lidocaine/Lignocaine infiltration numbs the puncture site completely. The patient remains 100% alert and oriented throughout.
Consciousness Level:Fully Awake & Alert
Subsequently, patient can talk normally, view coronary angiogram monitors, and listen to the interventional cardiologist in real time.
Breathing Reflexes:100% Unassisted & Spontaneous
Full airway protection maintained naturally; no oxygen mask or endotracheal support needed.
Sensation Experienced:Zero Sharp Pain
Indeed, numbing takes effect in <10 seconds. With this in mind, only painless tactile touch or subtle vibration felt during guide catheter exchange.
Post-Procedure Recovery:Zero Anesthesia Hangover
To clarify, no grogginess. In fact, patient can drink fluids, have a light meal, and mobilize safely within 15 to 30 minutes of radial band placement.
Specifically, Intravenous Conscious Sedation Standards & Anesthesia Care
Light Intravenous Anxiolysis: Carefully titrated low-dose intravenous anxiolytic (Midazolam) and mild analgesic (Fentanyl) produce deep physical calmness and relief from anxiety.
Furthermore, supplemental nasal cannula oxygen (2 L/min) provided with continuous pulse oximetry and capnography monitoring.
Sensation Experienced:Complete Absence of Stress & Discomfort
Additionally, patients report time feels like it passes very quickly with minimal to zero recall of contrast warmth or room sounds.
Post-Procedure Recovery:Clear Head Within 1 to 2 Hours
Consequently, mild grogginess clears quickly in the recovery lounge. Moreover, adult companion required to accompany patient home.
Consequently, General Anesthesia Indications & Complex Surgical Protocols
Selective Indication Protocol: Complete unconsciousness is NOT used for standard coronary angiography; it is strictly reserved for pediatric congenital procedures, severe dementia, or complex TAVI/mitral repairs.
In particular, endotracheal tube or laryngeal mask airway ensures dedicated airway control during complex structural cardiac repairs.
Sensation Experienced:Zero Awareness or Memory
For example, 100% amnesia and zero sensation during the entire procedure duration.
Post-Procedure Recovery:PACU Monitoring (3 to 5 Hours)
As a result, recovery takes place in the post-anesthesia care unit until protective reflexes, swallowing, and hemodynamics stabilize.
In addition, some patients experience a warm sensation when contrast material is injected. Notably, if sedation is used, it may help reduce anxiety and discomfort.
Accordingly, the experience differs from person to person. Similarly, patients should tell the clinical team immediately if they experience significant pain, breathing difficulty, or unusual discomfort during the procedure.
Meanwhile, contrast-induced acute kidney elevation, small pseudoaneurysm formation, or transient benign rhythm disturbances during catheter transit.
Notably, Clinical Safeguard: Pre-procedural serum creatinine/eGFR profiling, aggressive pre- and post-hydration, and ultrasound-guided vascular access.
Similarly, Major Events (MACE)As a result, Extremely Rare (< 0.08%)
Moreover, Major Cardiovascular Events
Subsequently, Coronary arterial dissection, acute myocardial infarction, embolic stroke, or emergency cardiac surgery during diagnostic catheterization.
Ultimately, Clinical Safeguard: ACC-NCDR registry adherence, live arterial waveform telemetry, IV heparinization, and instant cath lab interventional rescue capabilities.
The overall risk depends on the patient’s condition, the urgency of the procedure, kidney function, the type of catheterization, and whether an intervention is performed.
Indeed, the treating cardiologist should explain the expected benefits, material risks, and available alternatives before the procedure, except where emergency circumstances require immediate action.
Similarly, ALARA Radiation Protection & Kidney Shielding in Cardiac Catheterization
With this in mind, AERB-regulated institutional benchmarks maintaining minimum radiation exposure and contrast safety.
AERB Statutory Standards
Up to 60%
Pulsed Low-Dose Fluoroscopy
State-of-the-art C-arm system uses digital pulsed exposure (7.5–15 pulses/sec) rather than continuous beam, slashing cumulative radiation dose while preserving 4K coronary resolution.
Iso-Osmolar
Low-Osmolar Contrast Agents
To clarify, exclusively non-ionic, low-osmolar contrast media calibrated to patient body mass index and baseline eGFR levels to protect delicate renal tubules and eliminate allergic reactions.
0.5 mm Pb
Ceiling Scatter & Pelvic Shields
In fact, lead-acrylic suspended radiation barriers, thyroid shields, and bismuth organ covers minimize secondary scatter radiation to both patient and catheterization personnel.
Real-Time
Dose Area Product (DAP) Telemetry
Specifically, multi-channel ionization chambers measure real-time Gy·cm² dose exposure with automated alarms, fully documented in your permanent Henotic digital radiology record.
Minor & Self-Limiting Events: These transient reactions resolve spontaneously or with simple supportive care without long-term consequences.
~1.2% to 2.4%
In Particular, Localized Access Bruising (Ecchymosis)
Therefore, superficial skin discoloration at wrist or groin puncture; self-resolves within 7 to 10 days without treatment.
~0.8% to 1.5%
In Addition, Transient Contrast Heat Sensation
Warm feeling or mild metallic taste during arterial contrast injection; naturally subsides within 20 to 30 seconds.
~0.5% to 1.1%
Notably, Vasovagal Dizziness / Mild Slowing
In particular, transient lightheadedness during sheath removal or local pressure; quickly relieved by leg elevation and IV fluid bolus.
<0.5%
Similarly, Mild Skin Hives / Urticaria
For example, minor histamine skin reaction to contrast; treated promptly with a single dose of oral or IV antihistamine.
Rare Major Procedural Complications: In modern high-volume transradial cardiac catheterization centers, the incidence of major complications is extraordinarily low (<0.1%).
Under 0.05%
Ultimately, Vascular Pseudoaneurysm / Bleeding
As a result, arterial wall defect requiring ultrasound-guided thrombin injection or repair; practically eliminated with transradial access.
Approximately 0.06%
Overall, Contrast-Induced Acute Kidney Injury
In addition, transient serum creatinine rise in pre-existing renal disease; prevented by vigorous pre/post hydration and iso-osmolar dyes.
Less Than 0.05%
Meanwhile, Coronary Artery Dissection
Notably, intimal flap during catheter engagement; managed immediately with ad-hoc drug-eluting stent deployment.
Below 0.04%
Subsequently, Major Embolic Event (Stroke / MI)
Accordingly, micro-embolization from aortic plaques; minimized by heparin anticoagulation and careful wire manipulation techniques.
Henotic Diagnostics Multi-Tier Safety Protocols: Systematic safeguards embedded into every cardiac catheterization procedure.
89.4% Radial
Indeed, Transradial Access Primary Standard
Pioneering wrist-first approach virtually eliminates severe retroperitoneal groin hemorrhages and speeds ambulation.
Low Contrast
Clearly, Iso-Osmolar Contrast Calibration
Similarly, strict limitation of contrast volume to <3× eGFR (mL) combined with pre-procedure sodium bicarbonate infusion.
AERB Certified
Specifically, Digital Pulsed ALARA Dosimetry
In contrast, pulsed fluoroscopy (7.5–15 pps) cuts patient radiation by up to 60% compared to continuous analog systems.
Overall, recovery depends on the vascular access site, the procedure performed, the patient’s individual hemodynamic stability, and whether coronary stenting was performed.
Meanwhile, after the procedure, the clinical team monitors vital signs, access site hemostasis, and peripheral pulses in the affected limb.
In particular, Transradial (Wrist) Access
Additionally, Radial Artery Recovery Protocol
Primary clinical access route (>85% of cases) offering earlier ambulation and reduced bleeding risk.
Specifically, Bed Rest Time
Accordingly, 2 to 3 hours (Upright sitting permitted immediately)
Indeed, select a recovery phase below to review evidence-based clinical protocols, permitted activities, wound care rules, and return-to-work guidelines.
Moreover, Immediate Protocol 1: Direct Hemostasis, Monitoring & Hydration Protocol
Clinical Supervision
With this in mind, primary focus is securing absolute arterial seal at the access site, continuous hemodynamic rhythm monitoring, and eliminating radiopaque contrast media through high oral fluid hydration.
Specifically, Permitted & Prescribed Actions
Wrist Elevation: Furthermore, keep wrist in a neutral, supported resting position on a bedside arm pillow.
Contrast Dye Washout: Additionally, drink 1.5 to 2.0 Liters of water or oral fluids unless on strict heart-failure fluid limits.
Radial Band Protocol: Consequently, gradual deflation of the TR-Band (2 mL air released every 15 minutes by nursing staff).
Early Light Nutrition: Moreover, clear fluids or light meal once local sedation and nausea subside completely.
Furthermore, Strict Clinical Restrictions
No Puncture Site Flexion: Therefore, strictly avoid bending the wrist or pushing off bed with the punctured hand.
Strictly Zero Unassisted Ambulation: In particular, do not get out of bed without primary nurse supervision and stable blood pressure check.
Zero Heavy Gripping: Notably, do not lift luggage, mobile chargers, or heavy electronics using the punctured arm.
Femoral Access Rule: In addition, if groin access was utilized, maintain strict supine position with straight leg for 4–6 hours.
Additionally, Cath Lab Ward Monitoring Parameters
Radial Pulse Check: Accordingly, verification of distal radial/ulnar pulse and capillary refill (<2 seconds) every 15 mins.
Continuous ECG Telemetry: Similarly, sT-segment monitoring to confirm absence of procedural ischemia or arrhythmias.
Blood Pressure & O2 Saturation: Ultimately, automated non-invasive BP cycle every 30 minutes.
Discharge Readiness: Overall, ambulation trial without hematoma, dizziness, or vasovagal drop.
To clarify, following discharge, focus shifts to protecting the puncture seal, managing mild local tenderness, monitoring for unexpected swelling, and gradually resuming light household activities.
Specifically, Permitted & Prescribed Actions
Dressing Inspection: Meanwhile, keep the transparent sterile puncture dressing clean, intact, and dry for 24 hours.
Gentle Showering: Subsequently, quick lukewarm shower permitted after 24 hours; gently pat the site dry with a clean towel.
Light Ambulation: With this in mind, leisurely indoor walking is encouraged to stimulate circulation and prevent deep vein stasis.
Mild Pain Relief: Specifically, paracetamol (500–650 mg) as prescribed for localized wrist or groin tenderness.
Furthermore, Strict Clinical Restrictions
Water Submersion Restriction: Furthermore, strictly avoid bathtubs, swimming pools, hot tubs, or ocean bathing for 5 full days.
Physical Straining Prevention: Additionally, avoid vigorous coughing, heavy bowel straining, or lifting objects heavier than 2 kg.
Topical Care Protocol: Furthermore, do not scrub, apply ointments, powders, or herbal pastes over the puncture wound.
Zero Motor Vehicle Driving: Additionally, do not operate a car, motorcycle, or machinery for at least 48 hours post-sedation.
Critical Home Warning Signs (Call Hotline)
Expanding Hematoma: Consequently, any firm, rapidly growing lump under the puncture site exceeding a coin diameter.
Active Oozing: Moreover, continuous blood seepage that does not cease after 10 minutes of direct firm manual pressure.
Neurovascular Deficit: Therefore, pallor, coldness, tingling, or loss of sensory perception in fingers or toes.
Fever > 100.4°F (38°C): In particular, clinical indicator of potential superficial infection or thrombophlebitis.
Ultimately, Days 3 to 7 • Functional Resumption
In Particular, Functional Clearance 3: Work Resumption, Driving Guidelines & Daily Independence
Gradual Independence
Patients resume sedentary occupational activities, driving (subject to clinical verification), and expanded domestic tasks while continuing arterial protection and dual antiplatelet therapy.
Specifically, Permitted & Prescribed Actions
Desk & Office Work: Notably, resumption of computer work, typing, meetings, and light managerial duties.
Driving Clearance: In addition, resuming driving after 48 hours for diagnostic angiograms (7 days if coronary stent was deployed).
Moderate Walking: Accordingly, brisk flat-surface walking for 15–30 minutes daily to maintain aerobic conditioning.
Moreover, ask when it is safe to resume work, driving, exercise, and normal daily activities.
Meanwhile, Patient Discharge Protocol
Subsequently, Post-Catheterization Home Recovery Symptom Triage
Therefore, interactive 3-tier guidance for patients and caregivers following hospital discharge. In particular, select a severity level below to inspect immediate recommended actions:
Green: Expected Healing
Normal Post-Cath Symptoms
Ultimately, small dime-sized bruise at wrist or groin puncture
Overall, mild local ache manageable with oral paracetamol
Meanwhile, transient fatigue from conscious sedation medication
Specifically, Recommended Action: Routine home rest, drink 1.5–2L water to flush contrast dye, and keep sterile dressing dry for 24 hours.
Amber: Clinical Review
Prompt Doctor Notification
Subsequently, bruising or swelling expanding beyond original margin
With this in mind, body temperature exceeding 100.4°F (38°C) or mild chills
Specifically, persistent numbness, tingling, or cold sensation in fingers
Furthermore, Recommended Action: Call Henotic Cardiac Care Desk within 2 hours (+91 8879327184) for triage by the attending cardiologist.
Red: STAT Emergency
Immediate Emergency Triage
Furthermore, active bleeding or pulsing blood from puncture site
Additionally, rapidly expanding, firm, painful lump at access site
Consequently, recurrent chest tightness, pressure, or acute shortness of breath
Additionally, Recommended Action: Apply firm, continuous manual pressure directly over puncture site. Specifically, dial 108 or our 24/7 STAT emergency line (+91 8879327184) immediately.
For example, note: Recovery instructions differ for wrist and groin access and may be more restrictive after coronary intervention.
Overall, Comparative Modalities: Cardiac Catheterization vs. Other Heart Tests
Accordingly, different cardiac tests answer different clinical questions. Similarly, the appropriate investigation depends on the suspected condition and the information needed.
Clinical Fit Navigator
Clearly, Which Heart Test Do You Need? Cardiac Catheterization vs. Non-Invasive Tests
In contrast, select a clinical scenario below to see which diagnostic investigation is recommended by cardiologist consensus guidelines:
Ultimately, patients with recurring exertional angina (chest tightness during walking or climbing stairs) or a positive treadmill stress test (TMT) have suspected obstructive coronary artery disease. Overall, Cardiac Catheterization is the gold standard investigation.
Meanwhile, acute severe, crushing chest pain radiating to the left arm or jaw with ECG changes represents an ongoing myocardial infarction (heart attack). Subsequently, non-invasive tests are bypassed to prevent myocardial necrosis.
Why It’s Recommended:Moreover, Every minute of coronary occlusion causes irreversible heart muscle damage (“Time is Muscle”).
In Addition, Immediate Therapeutic Capability:Therefore, EMERGENCY STENT — Immediate guidewire crossing and aspiration thrombectomy/stenting.
Notably, Alternative Test Considered:In particular, None. CTCA and Stress Echo are contraindicated during active acute myocardial infarction.
Asymptomatic individuals with high risk profiles (diabetes, smoking, strong family history) or atypical non-cardiac chest sensations are best evaluated non-invasively first.
Why It’s Recommended:In addition, Outpatient 3D scan with 99% negative predictive value to reliably rule out obstructive coronary disease.
Similarly, Immediate Therapeutic Capability:Notably, Diagnostic Only — If severe plaque (>70%) is identified, referral for Cardiac Cath is required.
Ultimately, Alternative Test Considered:Similarly, Treadmill Stress ECG (TMT) or Stress Echocardiography for functional capacity assessment.
Primary Recommendation
Multimodality Evaluation
Overall, 2D Echocardiogram + Right Heart Catheterization
Patients with unexplained breathlessness, lower extremity swelling, or reduced ejection fraction require structural and pressure telemetry rather than just coronary imaging.
Why It’s Recommended:Ultimately, Echocardiogram assesses EF% and valves; Right Heart Cath measures pulmonary artery pressure directly.
Specifically, direct selective cinefluoroscopy with sub-millimeter arterial resolution (0.1 mm), intracardiac pressure telemetry, and fractional flow reserve (FFR).
Radiation ExposurePulsed ALARA (~2.0 – 5.0 mSv)
Subsequently, Diagnostic Accuracy100% Definitive Gold Standard
Indeed, Procedure Duration20 – 35 Minutes
Clearly, Intervention CapabilityImmediate Stenting (PCI) in Same Session
Furthermore, these tests are not interchangeable in every clinical situation. Additionally, Cardiac catheterization may be recommended when its findings are expected to provide information that non-invasive testing cannot adequately supply or when an invasive treatment may be needed.
Meanwhile, Who May Need Cardiac Catheterization? Clinical Candidacy Guide
Consequently, Cardiac catheterization is an invasive diagnostic and therapeutic procedure indicated when non-invasive tests require definitive anatomical verification or when direct intravascular pressure measurements are essential for treatment planning.
Specifically, Tier 1: STAT Priority
Generally, Emergency Indications for Urgent Cardiac Catheterization
Moreover, immediate primary catheterization indicated to re-establish coronary perfusion and limit myocardial damage.
Furthermore, Multidisciplinary Heart Team Review for Cardiac Catheterization Candidacy
Specifically, ACC / AHA & ESC Guideline Standard
Absolute Contraindications: In elective outpatient catheterization, an absolute contraindication means the procedure must NOT proceed until the acute life-threatening conflict is fully stabilized.
Active Severe Bleeding
Furthermore, Uncontrolled Hemorrhage or Severe Diathesis
For example, active gastrointestinal bleeding, acute hemorrhagic stroke, or refractory coagulopathy (INR > 4.5 unreversed) precludes elective vascular cannulation.
Contrast Anaphylaxis
Additionally, Severe Anaphylactoid Dye Allergy
As a result, documented prior anaphylactic shock / laryngeal edema to iodinated contrast without prior corticosteroid and H1/H2 antihistamine desensitization.
Refractory Hypoxia
Consequently, Acute Decompensated Pulmonary Edema
In addition, inability of the patient to lie flat in a supine position (orthopnea) without acute respiratory failure prior to endotracheal stabilization.
Informed Refusal
Moreover, Patient Non-Consent or Severe Delirium
Notably, absence of clinical consent or unmanageable patient agitation that renders high-precision fluoroscopy fluoroscopically hazardous.
Relative Delay Factors (Pre-Cath Optimization): Elective catheterization is deferred for 12 to 48 hours to medically stabilize correctable parameters, lowering procedural risk to baseline.
Renal Protective
Therefore, eGFR < 30 mL/min / Contrast Risk
Accordingly, managed with pre-procedural isotonic normal saline or IV sodium bicarbonate hydration; total contrast volume limited to <3× eGFR (mL).
Electrolyte Correction
In Particular, Hypokalemia / Digitalis Toxicity
Similarly, serum potassium < 3.5 mEq/L markedly increases catheter-induced ventricular fibrillatory risk; corrected via IV potassium infusion prior to cannulation.
Hemodynamic Control
Specifically, Severe Malignant Hypertension
In contrast, blood pressure > 180/110 mmHg is titrated down using IV labetalol or nitroglycerin to avoid catastrophic post-puncture vascular hematoma.
Sepsis Clearance
Notably, Active Systemic Febrile Illness
Ultimately, uncontrolled bacteremia or systemic infection poses risk of endovascular seeding; deferred until completion of targeted antibiotic therapy.
Heart Team Multidisciplinary Revascularization Framework: An Interventional Cardiologist and Cardiothoracic Surgeon jointly review anatomical catheterization films to determine PCI vs CABG vs OMT based on the SYNTAX Score.
SYNTAX Score ≤ 22
Similarly, Low Anatomical Complexity
In Addition, Primary Recommendation: Percutaneous Coronary Intervention (PCI) with Drug-Eluting Stents (DES).
Overall, single or two-vessel disease without chronic total occlusion. Meanwhile, long-term outcomes for PCI and CABG are equivalent with faster recovery from PCI.
Subsequently, 3-vessel disease without severe bifurcations. Indeed, if diabetic, CABG shows reduced repeat revascularization rates; if high surgical risk, multi-stent PCI preferred.
SYNTAX Score ≥ 33
Overall, High Complexity / Left Main
Similarly, Primary Recommendation: Coronary Artery Bypass Grafting (CABG) Surgery (AHA Class I).
With this in mind, severe diffuse multi-vessel calcification, chronic total occlusions, or bifurcated unprotected Left Main disease. To clarify, superior long-term survival with CABG.
Furthermore, the decision for catheterization is made in close partnership with your treating cardiologist, balancing clinical necessity, expected diagnostic yield, and individualized procedural safety.
In particular, Clinical Excellence & Regulatory Governance
In particular, adherence to national benchmarks in patient care governance, sterile surgical air filtration (HEPA filters), emergency resuscitation readiness, and informed clinical consent.
As a result, standardized quality management systems overseeing patient scheduling, contrast injection verification protocols, clinical documentation integrity, and post-procedure surveillance.
Quality Scope:Clearly, Total Quality Management in Healthcare
Verified Certifications
Specifically, Official Diagnostic Licenses & Accreditation Certificates
Furthermore, direct view of active clinical registrations and regulatory compliance certificates at Henotic Diagnostics.
AERB Medical RegistrationGenerally, Atomic Energy Regulatory Board
ISO 9001:2015 StandardsIn fact, Quality Management Systems
NABL Clinical Lab AccreditationAs a result, National Accreditation Board for Labs
ISOUG Diagnostic ProtocolAccordingly, Int’l Society of Ultrasound Guidelines
Statutory Health RegistrationSpecifically, PCPNDT Government Compliance
Furthermore, Audited Clinical Benchmarks
In addition, Cardiac Catheterization Quality Indicators & Safety Metrics
Notably, our catheterization laboratory strictly audits procedural safety, diagnostic accuracy, and radiation hygiene against international ACC/AHA and national NABH benchmarks:
Specifically, International Benchmark:ACC / AHA >70% Target
<58mConsequently, ↓ 32m Faster than Standard
Meanwhile, Door-to-Balloon Time (Emergency STEMI)
Similarly, average time from patient hospital arrival to balloon catheter inflation in acute myocardial infarction, saving critical heart muscle tissue.
Furthermore, International Benchmark:ACC / AHA <90 Min Standard
99.6%↑ Industry Leading
Subsequently, Contrast Nephropathy Prevention
In contrast, patients maintaining baseline renal function post-cath through iso-osmolar non-ionic contrast agents and protocolized pre/post saline hydration.
Furthermore, Medrad Mark 7 Arterion Hydraulic Injector
Subsequently, microprocessor-calibrated fluid management delivery unit that dispenses precise contrast volume at programmed rates with automated pressure cutoff safety relief.
Moreover, Flow Calibration:0.1 to 45.0 mL/sec (±0.1 mL)
Therefore, Air Detection:Dual Optical Air Bubble Sensors
In particular, Contrast Profile:Low-Osmolar Non-Ionic Agents
All fluoroscopic equipment operates with pulsed fluoroscopy (7.5–15 pulses/sec) rather than continuous beam exposure, reducing cumulative radiation dose by up to 60%. With this in mind, dose Area Product (DAP) meters continuously display patient milligray absorption on the primary surgical monitor.
Moreover, NABH Infection Control & Single-Use Consumable Assurance
To clarify, zero reuse policy: all diagnostic catheters, guide wires, radial sheaths, and balloon inflation devices are 100% single-use, sterile-packaged, and barcode-scanned to each patient’s electronic health record. In fact, the Cath Lab suite features HEPA-filtered laminar airflow maintaining Positive Pressure ISO Class 7 air cleanliness.
ISO Class 7 Laminar Airflow Theater 100% Barcode-Tracked Single-Use Devices Zero Procedural Sepsis Record
Specifically, every diagnostic coronary angiogram with borderline lesions (50%–70%) or multi-vessel involvement is evaluated by the multidisciplinary Heart Team (Interventional Cardiologist, Cardiothoracic Surgeon, and Non-Invasive Cardiac Imaging Specialist) to select the safest, most durable intervention.
Heart Team Case Conferences SYNTAX Score Risk Stratification 30-Day Post-Procedural Outcome Telemetry
Similarly, Continuous Clinical Quality Audits
Furthermore, all catheterization consumables, pre-lubricated diagnostic catheters, vascular sheaths, radiopaque contrast lots, and automated external defibrillators undergo batch-certified tracking in accordance with ISO 13485 and NABH infection control mandates.
Ultimately, Patient Financial Reassurance
Furthermore, Cashless Mediclaim Empanelment for Cardiac Catheterization Procedures
Additionally, dedicated institutional on-site TPA desk facilitating rapid pre-authorization, transparent policy coverage, and same-day cashless approvals for cardiac catheterization and coronary stenting.
Specifically, Private Mediclaim
In Particular, Retail Health Insurers
Consequently, star Health, Care Health, HDFC ERGO, ICICI Lombard, Niva Bupa, Aditya Birla Health, Tata AIG, Bajaj Allianz, and Reliance General.
Indeed, Direct Cashless Desk Empanelment
Furthermore, Institutional TPAs
Third-Party Administrators (TPAs)
Moreover, medi Assist, Paramount TPA, MD India, Vidal Health, Heritage Health, Raksha TPA, Family Health Plan (FHPL), and Health Insurance TPA.
Clearly, 2-Hour Rapid Pre-Auth Turnaround
Additionally, Public Sector Undertakings
In Addition, PSU Insurance Companies
Therefore, new India Assurance, United India Insurance, National Insurance Company, and Star Health Insurance Company.
Generally, Standard GIPSA Package Aligned
Notably, IRDAI Day-Care Procedure Eligibility: Zero 24-Hour Stay Required
Because radial cardiac catheterization is technologically advanced and performed under same-day monitoring (~4 to 6 hours), insurance coverage does not require 24 hours of hospital bed stay.
Specifically, Explicit Day-Care Inclusion:Furthermore, Coronary angiography is formally recognized under IRDAI listed day-care surgeries with standard reimbursement and cashless entitlement.
Consequently, Pre & Post Hospitalization Cover:As a result, All pre-procedure cardiac blood tests (creatinine, CBC) and 30-to-60 day post-procedure consultations are covered under standard policy terms.
Notably, Smooth Interventional Conversion:Accordingly, If diagnostic angiography proceeds to immediate stenting (PCI), cashless pre-authorization is seamlessly extended to include coronary stent implants.
Specifically, Required Patient Documents for Cashless Admission:
Similarly, active Health Insurance Card or Digital Policy E-Card
Ultimately, government Photo ID (Aadhaar Card / PAN Card / Passport)
Overall, cardiologist’s Written Advice / Admission Prescription
In particular, our dedicated insurance desk coordinates directly with your insurer’s medical underwriting team to submit claim forms and discharge summaries on your behalf.
For example, discover how our advanced fluoroscopic accuracy, gentle wrist radial access, and compassionate nursing care empower patients across Navi Mumbai and Mumbai through safe, stress-free cardiac diagnostics.
Meanwhile, Verified Patient Recovery Experiences and Clinical Stories
Specifically, Verified Radial Patient
&As a result, ldquo;I was extremely anxious when my cardiologist advised a coronary angiogram for persistent chest discomfort. In addition, the cardiac team at Henotic Diagnostics made me feel completely at ease. Notably, they used wrist radial access, and the local anaesthesia was barely a pinch. Dr. Accordingly, siddharth Sonkamble walked me through my coronary scan results immediately after. Similarly, i was discharged the same afternoon with absolute peace of mind.”
Indeed, Interventional Review:Specifically, Dr. Siddharth Sonkamble, MD, DM
Furthermore, Verified Stenting Patient
&In contrast, ldquo;After an abnormal treadmill stress test, I required a definitive cardiac catheterization. Ultimately, the Cath Lab environment at Henotic was spotless, calm, and equipped with impressive fluoroscopy technology. Overall, the nursing staff kept monitoring my vitals continuously, and the whole procedure was finished in under 40 minutes. Truly a gold standard experience in cardiac care.”
Clearly, Interventional Review:Specifically, Dr. Siddharth Sonkamble, MD, DM
Notably, Senior Patient Care & Right Heart Catheterization Feedback
Additionally, Verified Senior Patient
&Meanwhile, ldquo;I had unexplained breathlessness for months and needed a right heart catheterization to measure pulmonary pressures. Subsequently, the doctors explained every preparatory step with immense patience. Indeed, during the procedure, I felt no pain at all, just slight pressure. With this in mind, their gentle clinical approach made what felt like an intimidating test completely manageable.”
&To clarify, ldquo;When my ECG showed signs of ischemia, Henotic Diagnostics arranged my cardiac catheterization without unnecessary delays. In fact, the clarity of their cineangiography scans pinpointed the exact location of narrowing. Dr. Sonkamble explained our next therapeutic options in plain language without rushing. Their professional integrity is truly commendable.”
Similarly, Ultra-Low Radiation Protocol Ultimately, AERB ALARA Compliance Overall, Zero Allergy Reaction
Furthermore, Interventional Review:Specifically, Dr. Siddharth Sonkamble, MD, DM
Moreover, Verified Emergency Patient
&Specifically, ldquo;My biggest fear about cardiac catheterization was the recovery period and potential bleeding. Furthermore, the medical team applied a specialized wrist compression band after catheter removal, and I had zero bruising. Additionally, the post-procedure observation ward was comfortable, quiet, and attentive. Consequently, i’m grateful for their compassionate and precise care.”
Additionally, Interventional Review:Specifically, Dr. Siddharth Sonkamble, MD, DM
Therefore, Verified Follow-Up Patient
&Moreover, ldquo;I chose Henotic Diagnostics for an elective coronary catheterization based on their AERB and NABH accreditations. Therefore, from the initial fasting instructions to the discharge summary, everything operated like clockwork. In particular, knowing that the Cath Lab followed rigorous international radiation and sterile protocols gave my family tremendous confidence.”
Clearly, Frequently Asked Questions About Cardiac Catheterization
For example, review comprehensive clinical answers to 13 essential patient inquiries regarding the procedure, pain management, risks, and recovery expectations.
Showing all 13 questions
As a result, its main purpose is to investigate cardiovascular conditions by examining coronary arteries, measuring pressures within the heart and pulmonary circulation, or obtaining other selected diagnostic information. In some cases, it also provides a route for treatment.
No. In addition, Coronary angiography is a specific imaging procedure that can be performed as part of cardiac catheterization. Notably, Cardiac catheterization is a broader term that includes other diagnostic and therapeutic procedures.
Accordingly, the duration varies with the type of procedure, the complexity of the findings, and whether treatment is performed. Similarly, the clinical team can provide a more appropriate estimate based on the planned procedure.
It is generally a minimally invasive procedure rather than open-heart surgery. However, it remains an invasive cardiovascular procedure with potential complications and requires appropriate clinical facilities and monitoring.
However, general anaesthesia is not routinely required for many standard diagnostic catheterization procedures. Ultimately, local anaesthesia is commonly used, with sedation when appropriate. Overall, the anaesthesia plan depends on the procedure and the patient’s clinical needs.
Meanwhile, Coronary angiography can identify narrowing or blockage in the coronary arteries. Subsequently, the significance of each finding depends on its location, severity, effects on blood flow, and the patient’s symptoms and other clinical findings.
No. Indeed, diagnostic catheterization does not automatically involve stent placement. With this in mind, a stent may be considered when coronary intervention is appropriate, based on the clinical findings, treatment strategy, and informed consent.
To clarify, follow the specific fasting and fluid instructions provided by the treating team. In fact, requirements can differ depending on the planned procedure, sedation, and individual health conditions.
Recovery may take several hours for initial monitoring, while full recovery and activity restrictions depend on the access site, the procedure, and whether treatment was performed. Follow the discharge instructions rather than a fixed timetable.
Specifically, kidney disease can increase the risk of contrast-associated kidney complications. Furthermore, the clinical team assesses kidney function and considers appropriate precautions, contrast use, and alternative approaches when indicated.
Moreover, Long-Term Recovery, Driving & Work Clearance Guidance
Additionally, it may be urgently indicated in selected patients with acute coronary syndromes, including certain heart attacks, or other serious cardiovascular conditions. Consequently, emergency decisions depend on clinical assessment and the expected benefit of immediate intervention.
Moreover, right heart catheterization primarily measures pressures and blood flow-related parameters on the right side of the heart and in the pulmonary circulation. Therefore, left heart catheterization can provide information about pressures on the left side and may be performed alongside coronary angiography, depending on the indication.
In particular, a qualified cardiologist or appropriate treating specialist makes the recommendation based on the patient’s clinical condition, test results, potential benefits, procedural risks, and available alternatives.
Overall, No questions match your search term
For example, have a question not listed here? As a result, speak directly with our clinical cardiology team at Henotic Diagnostics.
Therefore, ICMR & CSI Clinical Practice Recommendations
In Particular, AERB Diagnostic Radiation Safety Standards
Notably, Henotic Diagnostics emphasizes clear, understandable information to help patients and families discuss cardiac investigations with qualified healthcare professionals.
Accordingly, an informed approach to cardiac care includes:
Similarly, understanding why a particular test has been recommended.
In contrast, reviewing relevant medical history and previous diagnostic findings.
Ultimately, discussing the benefits, risks, and alternatives to invasive procedures.
Overall, following individualized preparation and recovery instructions.
Meanwhile, ensuring that diagnostic findings are interpreted in the context of the patient’s clinical condition.
Clearly, ACC / AHA Clinical Guideline Hierarchy for Cardiac Catheterization
Subsequently, every diagnostic recommendation and interventional threshold is classified according to international gold-standard clinical consensus tiers:
Indeed, definitive evidence that cardiac catheterization improves survival and clinical outcomes. With this in mind, applied in acute STEMI (<90m primary PCI), non-ST elevation ACS with high-risk features, and refractory angina.
To clarify, substantial evidence supports procedure value. In fact, applied in intermediate-risk coronary blockages where invasive Fractional Flow Reserve (FFR ≤ 0.80) or IVUS plaque imaging guides stenting.
Class III DirectiveUltimately, Zero Benefit / Potential Risk
Indeed, Clinical Restriction (“Not Recommended”)
Specifically, invasive catheterization is not recommended in completely asymptomatic patients with low pre-test clinical probability or normal stress testing, protecting patients from unnecessary invasive exposure.
Clinical Governance
Generally, Multidisciplinary Cardiac Catheterization Procedural Team
Furthermore, every cardiac catheterization at Henotic Diagnostics is conducted by a coordinated four-tier clinical unit.
01
Clearly, Primary Interventional Cardiologist
Overall, Lead Operator • MD, DM
Additionally, performs arterial cannulation, guides micro-catheters under fluoroscopy, records hemodynamics, and deploys drug-eluting stents.
Moreover, controls digital C-arm angulation, calibrates multi-channel pressure transducers, and monitors ALARA radiation dose exposure meters.
04
Additionally, Critical Care Cath Nurse
Indeed, ACLS/BLS Certified Hemostasis Nurse
Therefore, maintains sterile procedural field, manages IV lines and emergency medications, and oversees post-procedure TR-Band compression recovery.
Clearly, Clinical Evidence Synthesis
In fact, International Guidelines for Cardiac Catheterization: ACC, AHA, ESC & CSI
2026 Updated Directives
Specifically, ACC Class I (Strong)<Level of Evidence: A
Consequently, Acute Coronary Syndrome (STEMI & Very High-Risk NSTEMI)
In particular, immediate invasive coronary catheterization and primary percutaneous coronary intervention (PCI) within <90 minutes of medical contact is unanimously recommended by ACC/AHA and ESC guidelines to restore myocardial perfusion and reduce mortality.
As a result, Indication Class I (Strong)Level of Evidence: B-R
Moreover, High-Risk Non-Invasive Test Findings (TMT / Stress Echo)
Diagnostic catheterization is indicated in patients with demonstrable extensive ischemia (>10% left ventricular myocardium) on functional stress testing or refractory exertional angina despite guideline-directed medical therapy.
Accordingly, Clinical Class IIa (Moderate)Level of Evidence: B-NR
For example, when high Agatston calcium score (>400) creates blooming artifacts on CT scans, invasive angiography is recommended to definitively establish lumen patency.
Furthermore, Default Class I (Strong)<Level of Evidence: A
In Particular, Transradial Access as Standard Default Route
Both the European Society of Cardiology (ESC) and American Heart Association (AHA) designate transradial access as a Class I (Level A) recommendation over transfemoral access due to significant reductions in all-cause mortality, access-site bleeding, and major adverse cardiovascular events (MACE).
Specifically, Hemostasis Class I (Strong)Level of Evidence: B-R
In Addition, Patent Hemostasis Protocol for Radial Patency
As a result, post-procedure radial artery compression must use patent hemostasis (guided by reverse Barbeau test or pulse oximetry) to preserve radial artery blood flow during compression and prevent radial artery occlusion (RAO).
Furthermore, Physiological Class I (Strong)Level of Evidence: A
Notably, Physiological Functional Assessment in Intermediate Stenosis
In addition, invasive physiological assessment with Fractional Flow Reserve (FFR ≤0.80) or instantaneous wave-free ratio (iFR ≤0.89) is Class I recommended to evaluate intermediate coronary lesions (40% to 90%) without prior non-invasive documentation of ischemia before deciding upon stenting.
Additionally, Contraindicated Class III (Harm)Level of Evidence: B-R
Notably, deployment of drug-eluting stents in anatomically intermediate lesions with negative physiological functional reserve (FFR >0.80) provides no clinical benefit and exposes the patient to unnecessary in-stent restenosis risk.
The choice of investigation should always be guided by clinical need rather than the assumption that a more invasive test is necessarily better.
Consequently, Direct Interventional Cardiology Care
As a result, Discuss Your Cardiac Catheterization Pathway with Our Cardiology Desk
Whether you require an initial catheterization evaluation, a second opinion on an existing coronary angiogram CD, or post-procedure recovery support, select your pathway below for direct medical team triage:
Accordingly, designed for patients with chest discomfort, shortness of breath, unexplained fatigue, or positive stress test (TMT) / 2D Echo results needing definitive catheterization.
Overall, Coronary Angiogram CD Review & Revascularization Triage
Similarly, comprehensive review with Dr. In contrast, siddharth Sonkamble (DM Cardiology) for complex anatomical decisions: multi-vessel disease, bifurcation stenting vs CABG, and SYNTAX score evaluation.
Recommended Preparation Documents:
Specifically, DICOM cineangiogram CD or cloud imaging link
Meanwhile, Post-Catheterization Home Care & Medication Follow-Up
Ultimately, support for patients recovering from radial or femoral catheterization: wound assessment, hematoma evaluation, dual antiplatelet therapy questions, and return-to-work clearance.
Recommended Preparation Documents:
Consequently, henotic discharge summary & prescription list
Moreover, photo of access site (wrist/groin) if evaluating swelling or bruising
Therefore, current blood pressure & heart rate telemetry readings
In particular, Peer-Reviewed Clinical Literature & Institutional Guidelines
Accordingly,
Medical Authority and Trust References
Overall, the clinical guidance, procedure indications, safety data, and preparation protocols presented on this page are strictly synthesized from internationally accredited interventional cardiology registries, national institutes of health, and consensus clinical practice guidelines.
Furthermore, Coronary Angioplasty (PCI Following Cardiac Catheterization)
In particular, therapeutic balloon dilatation and advanced drug-eluting stent (DES) placement to restore physiological blood flow to ischemic myocardium.
Ultimately, Consult With Our Cardiac Catheterization Care Team
Whether you have immediate clinical inquiries regarding cardiac catheterization, coronary angiography preparation, or need a second opinion review with Dr. Overall, siddharth Sonkamble, our diagnostic navigation team is here to assist.
Specifically, Henotic Diagnostics – Corporate Headquarters & Flagship Cardiac Center
Meanwhile, centrally located in Kharghar, Navi Mumbai to coordinate rapid pre-catheterization diagnostic workups, emergency cardiac enzyme profiling, and seamless Cath Lab admissions across Navi Mumbai, Panvel, and the Mumbai Metropolitan Region.
Kharghar Metro (Line 1)450m • 4 Min Walk
Station Sector 14 exit; covered pedestrian walkway along D-Mart Road directly to Millennium Empire Business Park.
Overall, Harbour Rail Line1.8 km • 6 Mins
Kharghar Railway Station sharing auto and app-cab stand right outside platform 1 to Sector 15.
Meanwhile, Sion-Panvel Expressway800m • 2 Mins
Utsav Chowk flyover exit leading directly onto Central Park arterial road with basement patient drop-off.
Subsequently, Direct Emergency BayGround Floor • Zero Delay
Ramp-accessible zero-incline stretcher entry equipped for rapid ambulance transfer into cath observation suite.
Open 24/7 • Interventional Cardiac Hub
Overall, AERB • NABL • NABH • ISO Certified
Furthermore, Flagship Center Facility Address & Operating Hours
Facility AddressHenotic Diagnostics – Flagship Diagnostic CenterSecond floor, Millennium Empire, Business Park, Plot No 47, D Mart Rd, Sector 15, Kharghar, Navi Mumbai, Panvel, Maharashtra 410210
Meanwhile, Landmark: Opposite D-Mart Road • 4 Mins to Kharghar Metro Station
Subsequently, Operating Hours & STAT Cardiac Intake
Subsequently, continuous 24/7 processing for emergency Troponin-I, hs-cTn, Serum Creatinine / eGFR (contrast safety clearance), and PT/INR coagulation profiling.
Indeed, full pre-procedure workup including 12-Lead ECG, 2D Echocardiography with Color Doppler, Complete Hemogram, Renal Contrast Risk Profiling, and interventional cardiologist consultation coordination.
Clearly, Urgent Home Blood Collection
With this in mind, 24/7 doorstep phlebotomy across Kharghar, Belapur, Seawoods, Nerul, Vashi, and Panvel for mobility-restricted cardiac patients requiring urgent pre-procedure tests.
You can book your Cardiac Catheterization appointment at our Saki Naka center through multiple convenient channels: call us directly at 088793 27184, send a WhatsApp message for instant booking, or use the online booking form on our website. Walk-in appointments are also welcome based on slot availability. We recommend advance booking to ensure zero wait times.
Yes, Henotic Diagnostics Saki Naka is empanelled with all major insurance companies and TPAs (Third Party Administrators) including Star Health, ICICI Lombard, New India Assurance, HDFC Ergo, Max Bupa, Bajaj Allianz, and many more. We offer cashless processing for Cardiac Catheterization where applicable. Please carry your insurance card and a valid ID for seamless processing.
At Henotic Diagnostics Saki Naka, most Cardiac Catheterization reports are delivered within 2-6 hours for routine tests. Critical and urgent reports are expedited on a priority basis. All reports are delivered digitally via WhatsApp, email, and our secure online patient portal. Hard copies are also available at the center upon request. You will receive an SMS/WhatsApp notification the moment your report is ready.
Henotic Diagnostics Saki Naka operates 24 hours a day, 7 days a week, including Sundays and public holidays. This means you can schedule your Cardiac Catheterization at a time that is most convenient for you — early morning, late evening, or even overnight for emergency requirements. Our radiology and pathology departments maintain round-the-clock availability.
Yes, Henotic Diagnostics Saki Naka is fully accredited by NABL (National Accreditation Board for Testing and Calibration Laboratories) and ISO 9001:2015 certified. Our radiology equipment also complies with AERB (Atomic Energy Regulatory Board) safety standards. These accreditations ensure that every Cardiac Catheterization performed at our facility meets the highest national and international quality benchmarks for accuracy, safety, and reliability.
Local FAQs
Cardiac Catheterization in Saki Naka
Answers to the most common questions about Cardiac Catheterization services near Saki Naka.
Yes, Henotic Diagnostics offers Cardiac Catheterization services near Saki Naka, Central Suburbs. Our NABL-accredited centre provides accurate diagnostics with state-of-the-art equipment and experienced radiologists. Book your appointment today for priority service.
The cost of Cardiac Catheterization at Henotic Diagnostics starts from competitive rates. We offer up to 50% savings compared to market rates in Saki Naka, with no compromise on quality. Contact us at +91 8879327184 for the latest pricing.
You can book Cardiac Catheterization near Saki Naka by calling +91 8879327184 or booking online through our website. We offer instant confirmation, zero waiting time with prior booking, and WhatsApp report delivery for your convenience.
Yes, most Cardiac Catheterization reports at Henotic Diagnostics are available within 24 hours, with many delivered same day. Reports are shared digitally via WhatsApp and email, so patients in Saki Naka can access results quickly without revisiting the centre.
Also Available In Central Suburbs
Get Cardiac Catheterization at other Henotic Diagnostics centers near you
Henotic Diagnostics offers affordable Cardiac Catheterization services across Central Suburbs — including Kurla, Kurla West, Chembur, Chembur West, Chembur Camp, and 20 more locations. All centers feature NABL-accredited labs, AERB-certified equipment, and same-day digital report delivery.
Hyper-Local Service Coverage
Cardiac Catheterization in Saki Naka, PIN 400072
Official diagnostic service-area for Saki Naka and adjoining micro-neighbourhoods in Mumbai.
If you are looking for a highly accurate Cardiac Catheterization near Saki Naka, Henotic Diagnostics is your trusted partner. Easily accessible from all major points in Central Suburbs, our world-class facility combines highly experienced radiologists with state-of-the-art medical technology. Patients from Saki Naka consistently rate us 4.9/5 Stars (based on 760 reviews) for our compassionate care, zero wait times, and instant report delivery.
Frequently Asked Questions
How much does a Cardiac Catheterization cost in Saki Naka?+
The cost of a Cardiac Catheterization at our Saki Naka diagnostic center is highly competitive. We offer transparent pricing with zero hidden fees. Contact us directly for today's discounted rate.
How quickly can I get my Cardiac Catheterization reports in Central Suburbs?+
For patients visiting from Saki Naka and across Central Suburbs, Henotic Diagnostics guarantees fast turnaround times. Most Cardiac Catheterization reports are available the same day via secure WhatsApp delivery.
Is the Saki Naka center NABL & AERB accredited?+
Yes! Our entire facility serving Saki Naka maintains strict NABL, ISO, and AERB accreditations to guarantee 100% precision for your Cardiac Catheterization.