
 Radiation Safety
Atomic Energy Regulatory Board (AERB) Radiation Safety
Specifically, certified for radiation safety standards and equipment dosage calibration in interventional cardiac fluoroscopy.
Connecting to our secure server


Accurate, fast, and reliable diagnostic services near you in Kopar Khairane, Navi Mumbai. Experience state-of-the-art technology with same-day reporting.
Coronary angioplasty (also known as percutaneous coronary intervention or PCI) is a gold-standard, minimally invasive procedure designed to restore blood flow through narrowed or blocked heart arteries. In addition, this clinical resource provides evidence-based guidance on procedural techniques, drug-eluting stent placement, risk stratification, and recovery. Specifically, patients can explore comprehensive medical insights reviewed by certified cardiac specialists.
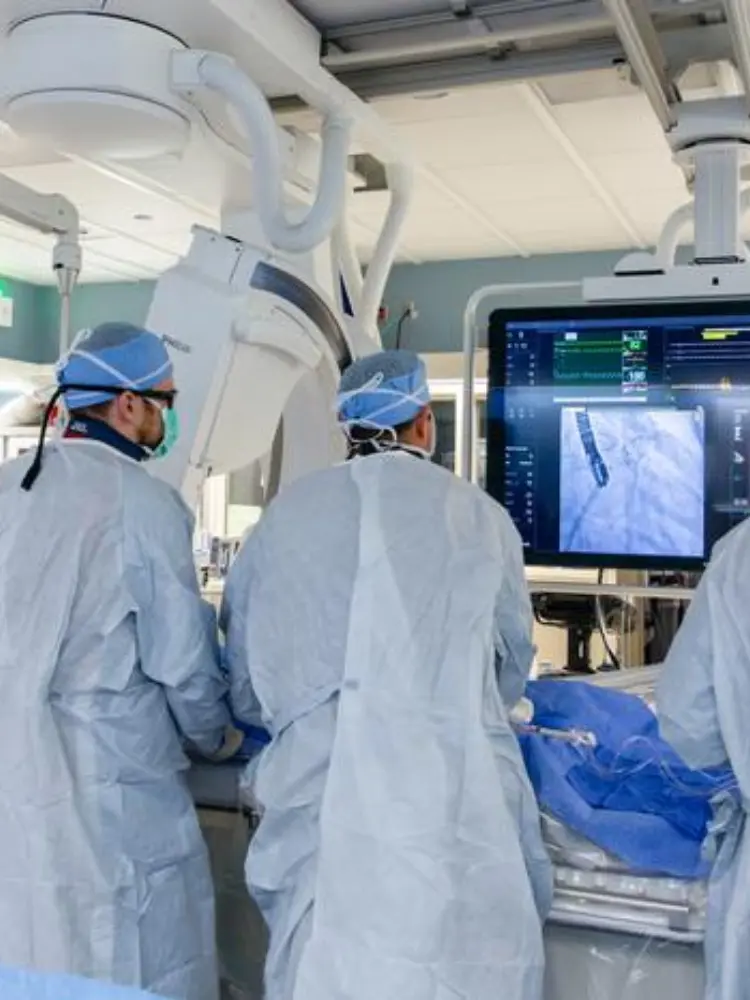
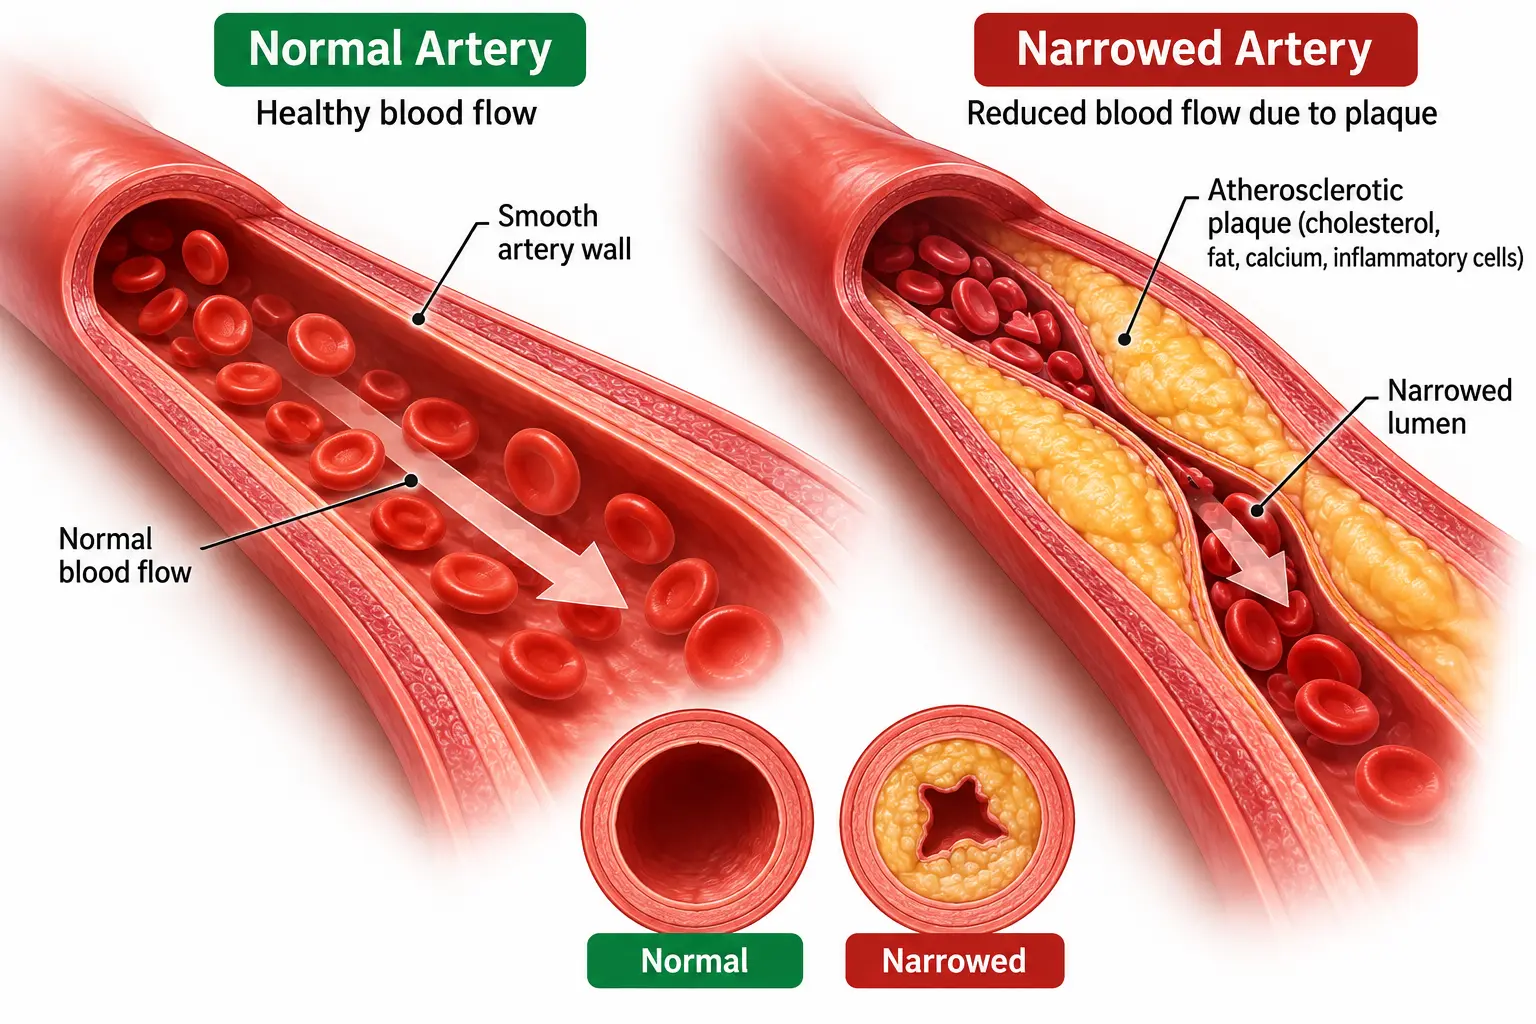
Specifically, coronary angioplasty is a minimally invasive medical procedure used to improve blood flow through narrowed or blocked arteries. In particular, it is commonly performed to treat coronary artery disease, in which the blood vessels supplying blood to the heart become narrowed due to plaque buildup.
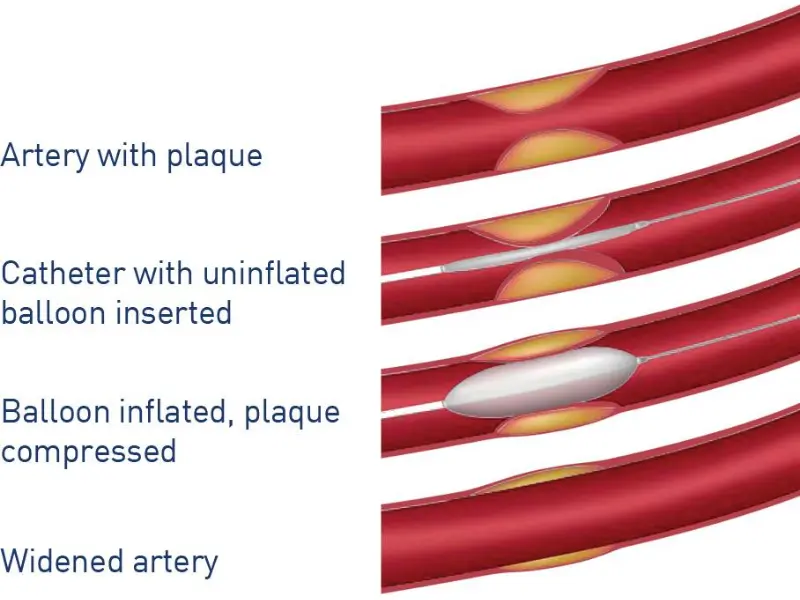
During coronary angioplasty, a specialist guides a thin catheter through a blood vessel to the affected artery. Furthermore, a small balloon is inflated to widen the narrowed area. In many cases, a small metal mesh tube called a stent is placed to help keep the artery open.
As a result, the procedure may help relieve symptoms such as chest pain and, in selected emergency situations, restore blood flow to the heart muscle. However, the appropriate treatment depends on the patient’s condition, test results and the treating cardiologist’s assessment.
Medical Definition & Overview
Angioplasty, also called balloon angioplasty, is a procedure used to open narrowed or blocked blood vessels. Specifically, coronary angioplasty treats arteries that supply blood to the heart.
In addition, a stent may be inserted during the procedure to support the artery and reduce the chance of it narrowing again. Consequently, angioplasty is performed by a trained interventional cardiologist in a specialised cardiac catheterisation laboratory.
Clinical Indications & Medical Rationale
Specifically, a cardiologist may recommend angioplasty when a significant narrowing in an artery is affecting blood flow or causing symptoms.
Golden 90-Minute Door-to-Balloon Window
Specifically, acute ST-segment elevation myocardial infarction (STEMI) demands urgent revascularization to salvage ischemic myocardium. In addition, our emergency primary PCI protocol ensures a Door-to-Balloon (D2B) time consistently under 90 minutes. Consequently, rapid restoration of coronary blood flow minimizes heart muscle necrosis and dramatically improves survival rates.
Immediate 12-lead ECG acquisition and direct Cath Lab team activation.
Rapid patient transfer to catheterization suite and sterile preparation.
Arterial puncture, guide catheter engagement, and culprit wire crossing.
Thrombus aspiration, balloon expansion, and drug-eluting stent placement.
Hemodynamic Unloading & Critical Survival Protocols
Specifically, acute heart attacks complicated by cardiogenic shock require immediate mechanical circulatory support during emergency coronary angioplasty. In addition, specialized microaxial pumps and balloon counterpulsation maintain systemic organ perfusion while the occluded coronary artery is reopened. Consequently, hemodynamic stabilization dramatically reduces 30-day mortality in critically ill cardiac patients.
Actively unloads the left ventricle up to 4.5 L/min, reducing myocardial oxygen demand per DanGer Shock trial evidence.
Synchronized counterpulsation elevates coronary diastolic perfusion and reduces ventricular afterload.
Extracorporeal membrane oxygenation provides full cardiopulmonary support in refractory cardiogenic arrest.
Specifically, clinical decision-making for angioplasty is grounded in landmark randomized controlled trials (RCTs) and international cardiology guidelines:
Demonstrates that invasive angioplasty significantly improves angina relief and quality of life in patients with severe ischemia.
Establishes PCI with Drug-Eluting Stents as an equivalent gold-standard revascularization strategy for Left Main lesions with low-to-intermediate SYNTAX scores.
Proves that culprit-lesion-only angioplasty reduces 30-day mortality in acute myocardial infarction with cardiogenic shock.
Class I-A recommendation for immediate primary PCI in acute coronary syndrome and physiological FFR/iFR guided stenting in chronic coronary syndromes.
Step-by-Step Procedural Protocol
Initially, the procedure generally involves the following sequential steps:
First, the medical team reviews symptoms, medical history, relevant investigations, kidney function when indicated, allergies and current medications.
Second, the catheter insertion site is numbed. In addition, sedation may be used when appropriate.
Third, a thin tube is introduced through an artery, commonly at the wrist or groin.
Fourth, imaging helps the cardiologist guide the catheter to the affected coronary artery.
Fifth, afterward, a small balloon is inflated to widen the narrowed section.
Sixth, subsequently, a stent may be deployed to help keep the artery open.
Finally, the patient is monitored for recovery and possible complications. Consequently, blood flow stability is verified before discharge.
Overall, the exact technique, duration and recovery period vary depending on the complexity of the procedure and the patient’s health.
Evidence From The Landmark MATRIX Trial (The Lancet)
Specifically, interventional cardiologists now prefer transradial access (via the radial artery in the wrist) over traditional transfemoral access (via the groin). In addition, large-scale clinical trials prove that radial access significantly lowers vascular complications. Consequently, over 90% of coronary angioplasty procedures at accredited cardiac care centers are performed via the wrist approach.
| Clinical Parameter | Transradial Access (Wrist) | Transfemoral Access (Groin) |
|---|---|---|
| Access Site Bleeding Risk | First, >70% reduction in major bleeding | Higher hematoma & bleeding risk |
| Post-Procedure Bed Rest | Second, immediate sitting; walk in 1 hour | Strict flat bed rest for 4 to 6 hours |
| Patient Comfort & Mobility | Third, high comfort; easy room movement | Back pain & restricted movement |
| Hospital Discharge Timeline | Overall, same-day or 24-hour discharge | 24 to 48 hours monitoring |
Advanced Microvascular Access Site Preservation
Specifically, preserving radial artery patency after coronary angioplasty is essential for patient comfort and future vascular access. In addition, our specialized Cath Lab protocol enforces patent hemostasis during wrist band compression. Consequently, radial artery occlusion rates are maintained below 1%, protecting the vessel for potential future interventions.
Routine intra-arterial Verapamil and Nitroglycerin administration completely eliminates arterial spasm during catheter manipulation.
Continuous Barbeau pulse oximeter monitoring confirms uninterrupted forward arterial flow during pneumatic TR Band inflation.
Controlled pneumatic air release every 15 minutes enables safe band removal within 2 to 3 hours without re-bleeding.
Comparison of Modern Coronary Stents & Balloons
Specifically, coronary stent engineering has evolved through three distinct technological generations to maximize safety and vascular healing. In addition, selecting the appropriate stent platform depends on arterial diameter, lesion length, and patient clinical profile. Therefore, modern interventional practices utilize thin-strut drug-eluting stents with biocompatible polymers.
First, coated with Everolimus or Zotarolimus to suppress tissue overgrowth. Features ultra-thin cobalt-chromium struts (<80 µm) with <2% long-term restenosis.
Second, constructed from polylactic acid that fully dissolves within 2 to 3 years, leaving the native artery uncaged to restore natural vasomotion.
Third, delivers antiproliferative Paclitaxel directly to the vessel wall without leaving behind a permanent metallic mesh. Ideal for In-Stent Restenosis (ISR).
Overall, uncoated stainless steel or cobalt mesh. Requires shorter DAPT duration but carries higher restenosis rates (15-20%), reserved for specific bleeding risks.
Precision Re-Intervention & Neoatherosclerosis Management
Specifically, recurrent arterial narrowing within a previously placed stent (In-Stent Restenosis or ISR) requires individualized lesion evaluation. In addition, high-definition intravascular imaging identifies whether the blockage is caused by tissue overgrowth or accelerated neoatherosclerosis. Therefore, cardiologists utilize non-stent technologies to restore vessel diameter without adding multiple metal layers.
Differentiates neointimal hyperplasia from stent under-expansion and calcified neoatherosclerosis.
Delivers antiproliferative Paclitaxel directly to the vessel wall, leaving no permanent metal behind.
Atherotome scoring disrupts fibrotic tissue resistance to ensure maximum luminal expansion.
High-Precision Functional & Anatomical Lesion Evaluation
Specifically, modern interventional cardiology utilizes advanced physiological and high-resolution intravascular imaging modalities during angioplasty. As a result, these technologies optimize stent sizing, verify strut expansion, and ensure maximum long-term vessel patency.
For instance, Fractional Flow Reserve (FFR < 0.80) and iFR (≤ 0.89) measure pressure gradients across intermediate coronary blockages (50–70% stenosis) to determine if a lesion is hemodynamically significant before deploying a stent. Therefore, unnecessary stenting is effectively avoided.
In addition, IVUS provides a 360-degree cross-sectional acoustic view of the vessel wall. Consequently, it helps cardiologists assess plaque burden, measure exact vessel diameter, and confirm complete stent apposition against the arterial wall.
Furthermore, OCT uses near-infrared light to generate microscopic 10-micron resolution imaging. In contrast to standard X-ray imaging, OCT visualizes thin-cap fibroatheroma (TCFA), calcium thickness, and micro-dissections with unmatched optical clarity.
Specifically, specialized antegrade and retrograde microcatheter dissection techniques enable revascularization of 100% chronically occluded coronary arteries.
In addition, advanced double-stenting techniques (DK-Crush, Culotte, and T-stenting) restore unobstructed flow to complex arterial junctions.
Furthermore, Intravascular Lithotripsy (IVL) and Rotational Atherectomy disrupt deep vessel calcium prior to safe stent expansion.
Atypical Myocardial Infarction Diagnostic Pathways
Specifically, not all acute cardiac syndromes stem from traditional atherosclerotic plaque blockages. In addition, Spontaneous Coronary Artery Dissection (SCAD) and Myocardial Infarction with Non-Obstructive Coronary Arteries (MINOCA) require distinct interventional triage. Therefore, our cardiology team utilizes advanced intravascular imaging to prevent unnecessary stenting in fragile arterial walls.
First, frequently occurs in younger women without cardiovascular risk factors. Furthermore, conservative medical healing is preferred over stenting unless ongoing ischemia persists, avoiding intramural hematoma propagation.
Second, evaluated using high-resolution OCT and Cardiac MRI to identify coronary vasospasm, microvascular resistance, or myocarditis. As a result, patients receive targeted therapy without unneeded stent placement.
Advanced Patient Safety & Renal Protection Standards
Specifically, modern catheterization laboratories strictly adhere to international ALARA guidelines (As Low As Reasonably Achievable) to minimize X-ray radiation exposure. In addition, specialized zero-contrast and ultra-low contrast PCI protocols protect kidney function in patients suffering from Chronic Kidney Disease (CKD Stage 3b/4). Consequently, procedural safety is maximized for high-risk patients.
First, digital flat-panel detectors and ultra-low pulse fluoroscopy reduce radiation dose by up to 60%. Furthermore, automated collimation and real-time Dose Area Product (DAP) monitoring protect both patient and medical team.
Second, intravascular ultrasound (IVUS) wire co-registration allows stent sizing and balloon expansion without radiopaque dye. As a result, contrast-induced nephropathy risk is virtually eliminated in vulnerable renal failure patients.
Drug-Eluting Stents (DES) & Blood Thinner Management
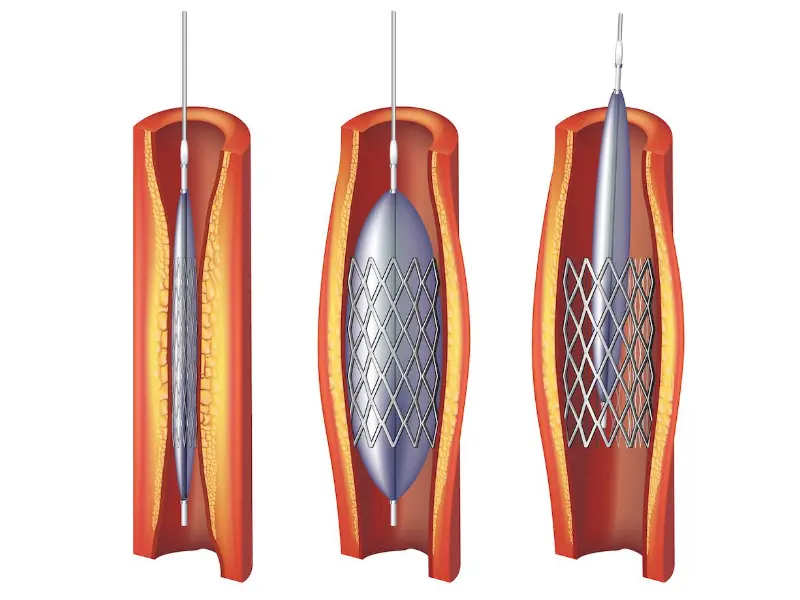
Specifically, modern angioplasty utilizes 2nd and 3rd generation Drug-Eluting Stents engineered with ultrathin platinum-chromium or cobalt-chromium struts (< 81 μm). In addition, these stents are coated with antiproliferative agents (such as Everolimus, Zotarolimus, or Sirolimus) embedded in bioresorbable polymers.
Furthermore, after stent placement during angioplasty, patients must adhere strictly to Dual Antiplatelet Therapy (DAPT) to prevent acute or late stent thrombosis:
Overall, DAPT duration is tailored using the Academic Research Consortium for High Bleeding Risk (ARC-HBR) framework to balance ischemic protection against bleeding safety:
12 months of full DAPT in Acute Coronary Syndrome (ACS) or 6 months in chronic stable angina.
Abbreviated 1-to-3 month DAPT followed by monotherapy, significantly reducing bleeding complications.
Wrist-First Catheterization & Surgical Treatment Selection
Specifically, over 90% of coronary angioplasty procedures are performed via Transradial Access (through the radial artery at the wrist). In contrast to femoral access, this approach offers significant clinical advantages:
In addition, for multi-vessel coronary disease, the Heart Team uses the SYNTAX Score to evaluate whether angioplasty (PCI) or Bypass Surgery (CABG) is optimal:
Diagnostic vs. Therapeutic Clinical Comparison
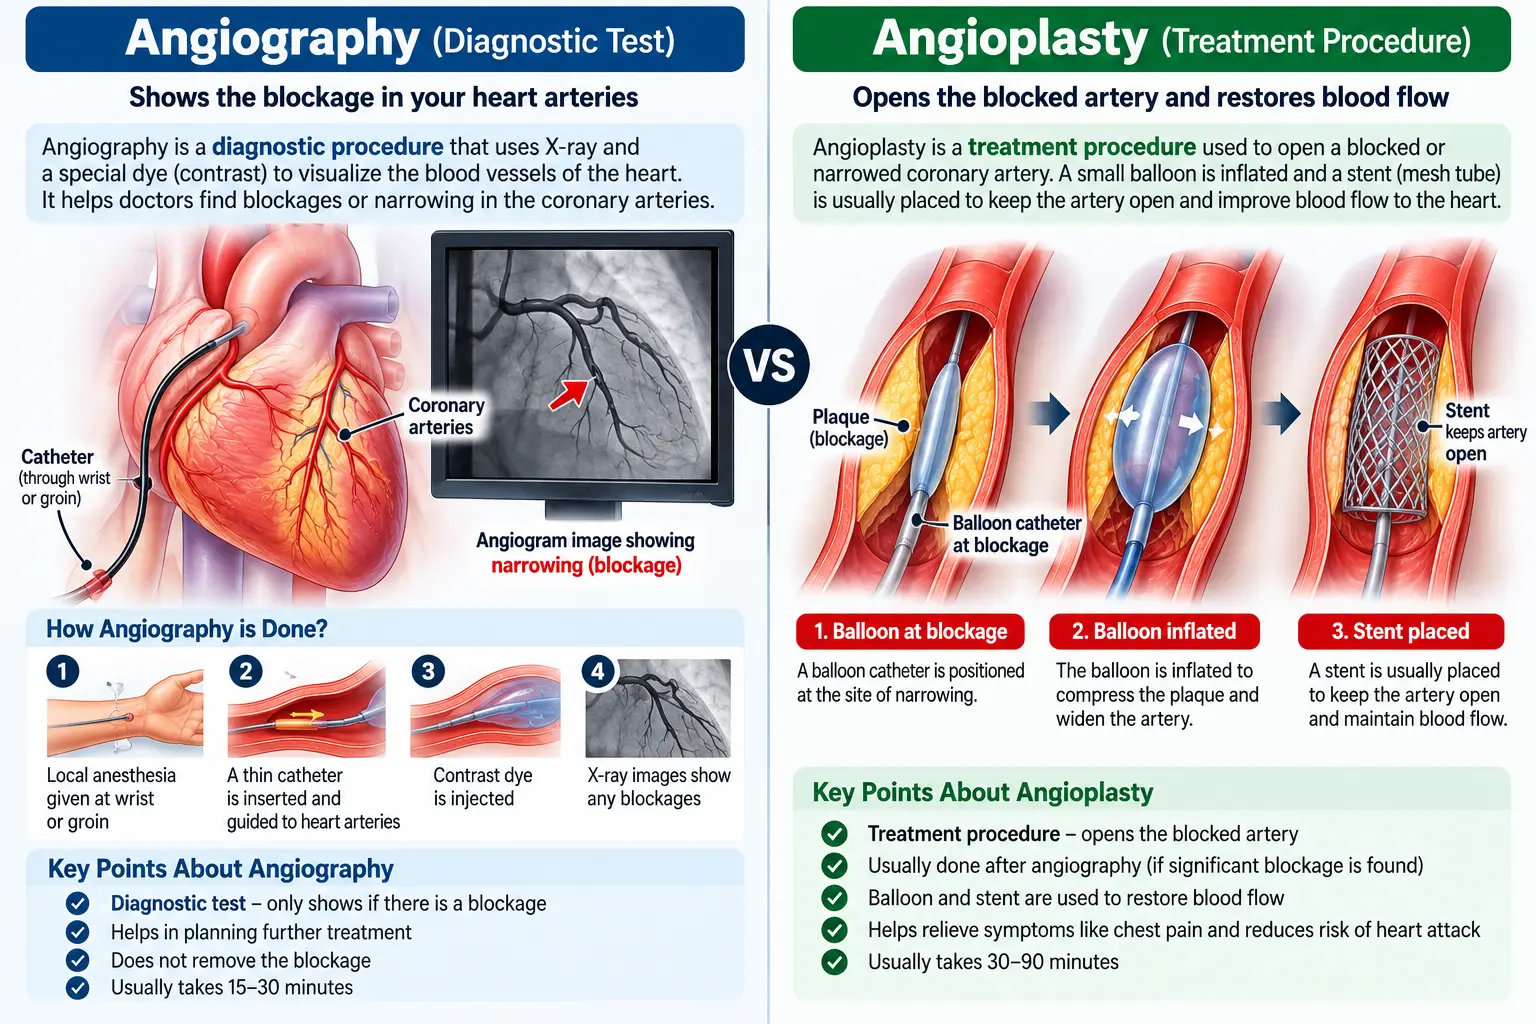
Specifically, angiography and angioplasty are related but different procedures. First, angiography identifies vascular blockages. In contrast, angioplasty therapeutic restores blood flow.
| Feature | Angiography | Angioplasty |
|---|---|---|
| Main purpose | Examines blood vessels and identifies narrowing or blockage | Opens a narrowed or blocked artery |
| What happens | Contrast dye and X-ray imaging show blood flow | A balloon is inflated; a stent may be placed |
| Is a stent required? | No | May be required |
| Role | Primarily diagnostic | Primarily therapeutic |
In addition, coronary angiography may be performed first to identify the location and severity of a blockage. Subsequently, angioplasty may be performed during the same session when clinically appropriate and planned by the treating team.
Clinical Efficacy & Outcomes
Overall, potential benefits depend on the patient’s condition and the reason for treatment. Specifically, they may include:
Safety Profile & Potential Complications
Specifically, angioplasty is commonly performed, but it carries potential risks. For example, these may include bleeding or bruising at the catheter insertion site, blood vessel injury, allergic reaction to contrast dye, kidney-related complications, abnormal heart rhythms, blood clots, heart attack, stroke or, rarely, death.
However, the likelihood of complications varies according to the patient’s health, kidney function, the urgency of treatment and the complexity of the procedure. Therefore, the treating cardiologist should explain the individual risks and expected benefits before a planned procedure.
In particular, for patients with Chronic Kidney Disease (CKD) or diabetes undergoing angioplasty, strict nephroprotection protocols are enforced:
Pre- and post-procedural 0.9% Isotonic Saline infusion expands intravascular volume and accelerates contrast clearance.
Furthermore, the utilization of non-ionic iso-osmolar contrast media minimizes renal tubular cytotoxicity and osmotic diuresis.
Consequently, strict volumetric restriction of total contrast media ($V/\text{eGFR} < 3.0$) effectively eliminates contrast-induced nephropathy risk.
Cardio-Renal Metabolic Protection & Glycemic Optimization
Specifically, diabetic patients presenting with coronary artery disease exhibit unique microvascular considerations and diffuse calcification. In addition, strict peri-procedural medication safety protocols prevent contrast interactions. Consequently, Henotic Diagnostics enforces standardized metabolic guidelines per the latest ESC Diabetes and Cardiovascular Disease directives.
Metformin is withheld on procedure day and for 48 hours post-PCI until renal eGFR stability is re-verified, eliminating lactic acidosis risk.
Guideline-directed initiation of Dapagliflozin or Empagliflozin significantly reduces recurrent major adverse cardiac events (MACE).
Long-term secondary glycemic management protects microvascular stent patency and inhibits downstream arterial disease progression.
Post-Procedural Healing & Precautions
Overall, recovery depends on whether angioplasty was planned or performed during an emergency, the access site used and the patient’s overall health.
For instance, some patients can return home relatively soon after an uncomplicated procedure, while others require longer hospital monitoring. In addition, the healthcare team provides instructions about activity, wound care, follow-up appointments and returning to normal activities.

Specifically, structured cardiac rehabilitation guides patient recovery across three distinct phases:
TR Band deflation schedule, arm immobilisation for 2–4 hours, telemetry monitoring, and early ambulation.
Supervised exercise testing, MET progression (building from 2 METs to 5 METs), and DAPT adherence verification.
Independent aerobic exercise (MET > 7), dietary optimization, stress management, and lipid target maintenance.
In particular, patients must take prescribed medicines exactly as directed. Specifically, antiplatelet medicines (Aspirin plus Ticagrelor, Clopidogrel, or Prasugrel) that prevent blood clots in a stent must NEVER be paused or stopped without direct guidance from the treating interventional cardiologist due to catastrophic acute stent thrombosis risk.
Furthermore, after angioplasty, patients are generally advised to adhere to the following guidelines:
Patient Self-Care & Secondary Prevention Guidelines
Specifically, never discontinue, interrupt, or alter your prescribed Dual Antiplatelet Therapy (Aspirin plus Ticagrelor, Clopidogrel, or Prasugrel) without explicit direct instruction from your treating interventional cardiologist. As a result, abrupt cessation—even for a few days or prior to dental or minor surgical procedures—drastically elevates the risk of catastrophic acute stent thrombosis, acute myocardial infarction, or death. Therefore, if any other physician or dentist advises stopping your blood thinners, call our cardiology team immediately at 088793 27184 before making changes.
Specifically, strict adherence to dual antiplatelet therapy (DAPT) and lifestyle modifications prevents stent thrombosis and recurrent arterial blockages. Therefore, complete the daily compliance checklist below to maintain optimum recovery metrics.
Patient Fit-to-Fly Certification & Practical Guidelines
Specifically, patients recovering from coronary angioplasty frequently have practical questions regarding flying, security scanners, and medical imaging. In addition, international cardiology consensus statements provide clear safety timelines. Consequently, patients can travel with complete confidence following specialist discharge clearance.
Uncomplicated elective angioplasty permits commercial air travel after 48–72 hours; uncomplicated STEMI allows flying after 10–14 days.
Coronary stents are manufactured from micro-thin platinum-chromium alloys and never trigger airport security metal detectors.
Modern drug-eluting stents are certified 100% MRI Conditional, allowing safe scanning up to 3 Tesla immediately post-procedure.
Patients receive a wallet-sized stent identification card specifying stent dimensions, date, and required DAPT regimen.
Evidence-Based Cardiovascular Risk Reduction Guidelines (ESC / ACC / AHA)
< 55 mg/dL
For example, achieved via High-Intensity Statins + Ezetimibe ± PCSK9 inhibitors.
< 130 / 80 mmHg
In addition, managed using ACE-i / ARB & Beta-Blocker therapy post-PCI.
HbA1c < 7.0%
Furthermore, preferring SGLT2 inhibitors or GLP-1 RAs with proven CV benefits.
Phase 1 – 3 Program
Finally, structured aerobic exercise training and risk counseling.
ESC & ACC/AHA/SCAI Guideline-Driven Revascularization Triage
Specifically, complex coronary artery disease cases undergo formal review by a Multidisciplinary Heart Team comprising an Interventional Cardiologist, Cardiothoracic Surgeon, and Non-Invasive Specialist. In addition, the SYNTAX score is calculated to objectively determine whether Angioplasty (PCI) or Coronary Artery Bypass Grafting (CABG) yields superior long-term outcomes.
First, PCI with drug-eluting stenting is the preferred Class I recommendation. In addition, it offers equal survival benefit to surgery with faster recovery and zero sternotomy incision.
Second, individual Heart Team consensus recommendation based on diabetic status, left ventricular function, radial access feasibility, and patient preference.
Third, CABG surgery is evaluated for severe diffuse 3-vessel disease. However, high-risk PCI with mechanical circulatory support (Impella/IABP) is offered when surgery is contraindicated.
Fast 24-Hour Digital DICOM Review by Heart Team Specialists
Specifically, patients who have already undergone coronary angiography elsewhere can easily submit their diagnostic CD or DICOM files for an independent specialist second opinion. In addition, Dr. Siddharth Sonkamble and the multidisciplinary Heart Team review lesion morphology, functional FFR indicators, and revascularization suitability. Consequently, patients receive an objective recommendation on whether angioplasty or medical therapy is ideal.
Upload raw DICOM angiogram files securely or courier your angiography CD to our Kharghar corporate office.
Senior interventional cardiologists independently measure arterial stenosis percentage and calculate SYNTAX scores.
Receive a detailed written second opinion report and a virtual tele-consultation explaining all procedural options.
Clinical Excellence, Safety Protocols & Precision Benchmarks
Specifically, our interventional cardiology unit operates under rigid clinical quality controls and radiation safety benchmarks. As a result, patients receive standardized, evidence-based care across all diagnostic and therapeutic angioplasty procedures.
First, strict compliance with Atomic Energy Regulatory Board (AERB) ALARA guidelines ensures minimized fluoroscopic X-ray exposure for patients and clinical staff during angioplasty.
Second, catheterization lab sterilisation, infection surveillance, and pre-operative cardiac diagnostics adhere 100% to NABH and NABL national quality standards.
Third, certified ISO management workflows guarantee systematic quality verification across patient intake, stent deployment, and post-angioplasty recovery monitoring.
Fourth, diagnostic vascular ultrasound and echocardiography equipment undergo daily acoustic calibration per ISUOG International Imaging Guidelines.
Finally, full statutory registration and strict adherence to ethical diagnostic practices under PC-PNDT Statutory Regulations guarantee institutional integrity and complete patient trust.
Specifically, our interventional catheterization laboratory benchmarks clinical safety metrics against global interventional cardiology registries. In addition, continuous monitoring ensures minimized procedural exposure for all coronary angioplasty patients.
< 11.5 Minutes
Maintained significantly below international diagnostic reference levels.
< 28.5 Gy·cm²
Optimized ultra-low pulse fluoroscopy ensures minimal X-ray scatter.
< 2.2 Ratio
Strict volumetric rationing guarantees nephroprotective kidney safety.
Nationally & Internationally Recognized Quality Benchmarks
In addition, our medical institution maintains official accreditations and certifications from leading statutory bodies and international healthcare quality councils. Consequently, patients can verify our certified credentials below:
Radiation Safety
Specifically, certified for radiation safety standards and equipment dosage calibration in interventional cardiac fluoroscopy.
 Clinical Quality
In addition, accredited by NABH for hospital excellence, patient safety protocols, and certified catheterization procedures.
 ISO 9001:2015
Furthermore, certified ISO 9001:2015 quality management system covering overall clinical and diagnostic operations.
 Statutory Ethics
Consequently, fully registered and certified for diagnostic compliance under PC-PNDT statutory requirements.
 Ultrasound Society
Overall, certified by the International Society of Ultrasound for advanced diagnostic Doppler and imaging standards.
Comprehensive clinical background, verified procedural credentials, and specialist consultation details for senior interventional cardiologist Dr Siddharth Sonkamble.
Specifically, as an interventional cardiologist, Dr Siddharth Sonkamble specializes in complex coronary angioplasty, radial access stenting, emergency primary PCI, intravascular imaging (IVUS/OCT), and comprehensive post-procedure cardiac rehabilitation. In addition, he provides evidence-based consultation for complex coronary revascularization.
MBBS, MD (Medicine), DM (Cardiology)
Doctor of Medicine in Advanced Cardiology
FESC & FSCAI
Fellow of European Society of Cardiology & SCAI (USA)
Complex PCI & Stenting
Radial Access, Left Main, Bifurcation & CTO
IVUS, OCT & FFR Precision
High-Resolution Plaque & Stent Expansion Analysis
Have you already undergone coronary angiography? Submit your DICOM CD for an independent review by Dr. Sonkamble and the Heart Team.
Furthermore, read real feedback from patients who completed coronary angioplasty and cardiac evaluation with us.
“To begin with, I suffered severe chest pressure and shortness of breath and needed an urgent coronary angioplasty evaluation. As a result, the cardiology team guided me through the transradial stenting procedure smoothly, restoring blood flow immediately.”
“Furthermore, the Cath Lab staff made sure I was completely comfortable during the wrist access procedure and post-op recovery monitoring phase. Highly recommended for cardiac patients!”
“In addition, they delivered rapid diagnostic reporting within 3 hours. Consequently, printed angiography laser films and digital DICOM links were provided right away for my cardiologist.”
State-of-the-Art Clinical & Diagnostic Facility
Specifically, our medical facility features modern diagnostic infrastructure, high-precision laboratory equipment, and comfortable patient reception areas. In addition, state-of-the-art diagnostic suites support optimal patient care.

First, patient registration and dedicated onboarding desk.

Second, spacious comfortable waiting lounge for families.

Furthermore, fully equipped cardiac diagnostic center building.

Finally, nationally accredited diagnostic pathology laboratory.
Preparation, Diagnostics & Rehabilitation
Overall, patient education plays a vital role in procedural success and long-term recovery. Specifically, patients can review key preparatory steps and diagnostic requirements below:
Evidence-Based Triage Guidance & Procedure Readiness Evaluator
Specifically, review this 4-step clinical self-assessment to evaluate your cardiovascular symptom severity and identify whether immediate specialist intervention, diagnostic angiography, or routine elective evaluation is clinically indicated.
| Score Range | Clinical Risk Level | Recommended Clinical Protocol & Next Steps |
|---|---|---|
| Score 0 – 2 | ✓ Lower Risk / Elective | Specifically, guideline-directed medical therapy (GDMT) and preventive lifestyle care are advised, along with an annual clinical checkup featuring resting ECG, lipid profile, and non-invasive follow-up. |
| Score 3 – 5 | ⚠️ Moderate Risk | In addition, a comprehensive outpatient cardiology consultation is recommended within 48–72 hours, alongside functional ischemia evaluation using TMT, 2D Echocardiogram, or CT Coronary Angiogram. |
| Score 6 – 11 or ANY Rest Pain | 🚨 High / Urgent Priority | URGENT CARDIOLOGY EVALUATION REQUIRED. Consequently, hospital emergency admission protocol is initiated for immediate diagnostic coronary angiography and primary or early Percutaneous Coronary Intervention (PCI). |
Specifically, if you or someone nearby is experiencing sudden crushing chest pressure, pain radiating to the left arm, neck, or jaw, cold sweating, or severe breathlessness: DO NOT WAIT OR RELY ON ONLINE FORMS. Therefore, immediately call our 24/7 Cardiac Emergency Helpline at 088793 27184 or proceed to the nearest emergency cardiac center.
* Mandatory Medical Notice: This clinical guidance matrix is for informational self-triage only and does not replace in-person diagnosis by a qualified interventional cardiologist. Therefore, if you experience severe chest discomfort, seek immediate medical care.
Direct Answers for Patients & Families
In short, no, because coronary angioplasty is a catheter-based procedure performed through a blood vessel. In contrast, coronary artery bypass surgery is an open-chest operation that creates an alternative route for blood to flow around blocked arteries. Therefore, the appropriate option depends entirely on the patient’s coronary anatomy and clinical condition.
In general, no, although a stent is frequently deployed during coronary angioplasty, because the final decision depends on vascular anatomy, lesion calcification, and treatment strategy. Consequently, some patients may receive drug-coated balloon angioplasty alone.
Specifically, yes, because primary angioplasty serves as the urgent gold-standard treatment for acute heart attacks by rapidly restoring blood flow to the ischemic myocardium. However, emergency treatment should never be delayed while searching for online information.
Overall, the procedural duration varies according to the complexity of the arterial blockage, the number of vessels treated, and whether intravascular imaging is utilized. Therefore, the treating cardiac team provides a personalized estimate for each patient.
Unfortunately, yes. The treated area or other arteries may develop further narrowing. However, stents reduce the risk of the treated segment narrowing again, but they do not eliminate it. Consequently, medication adherence and long-term cardiovascular care are essential.
In short, age alone does not determine whether angioplasty is suitable. Rather, the cardiologist considers overall health, other medical conditions, kidney function, the severity of the blockage and the likely benefits and risks.
Overall, neither option is best for every patient. Instead, the choice depends on the number and location of blocked arteries, the complexity of coronary disease, heart function, other medical conditions and the patient’s preferences after discussion with the heart team.
Specifically, assessment may include an ECG, blood tests, echocardiography and coronary angiography, depending on the clinical situation. In addition, additional tests are selected according to the patient’s symptoms and medical history.
Emergency Red-Flag Symptoms
In particular, new, severe or persistent chest discomfort, particularly when accompanied by breathlessness, sweating, nausea or faintness, may indicate a medical emergency. Therefore, call your local emergency service immediately rather than waiting for a routine appointment or an online response.
Specifically, this content is intended for general educational purposes and does not replace an in-person consultation with a qualified cardiologist. In addition, angioplasty clinical decisions, procedure timing, medication selection, dosages, treatment duration, target LDL-C goals (< 55 mg/dL), and rehabilitation plans must be individualized by the treating cardiologist and hospital clinical team. Specifically, prescribed dual antiplatelet therapy must never be discontinued without direct clinician instruction. Overall, all clinical protocols reference ACC/AHA/SCAI Coronary Revascularization and ESC Myocardial Revascularization Guidelines.
If you or a loved one requires high-precision angioplasty evaluation, coronary stenting assessment, 2D Echo, or cardiac diagnostic review, do not delay. In addition, contact our specialized interventional cardiology team today to schedule your consultation.

Second floor, Millennium Empire, Business Park, Plot No 47, D Mart Rd, Sector 15, Kharghar, Navi Mumbai, Panvel, Maharashtra 410210
Phone: 088793 27184 | Hours: Open 24 Hours
Coronary Stenting, Angiography Review & Interventional Cardiology Care
Priority service for Kopar Khairane patients.
Answers to the most common questions about Angioplasty services near Kopar Khairane.
Get Angioplasty at other Henotic Diagnostics centers near you
Henotic Diagnostics offers affordable Angioplasty services across Navi Mumbai — including Vashi, Sanpada, Juinagar, Nerul, Seawoods, and 10 more locations. All centers feature NABL-accredited labs, AERB-certified equipment, and same-day digital report delivery.
If you are looking for a highly accurate Angioplasty near Kopar Khairane, Henotic Diagnostics is your trusted partner. Easily accessible from all major points in Navi Mumbai, our world-class facility combines highly experienced radiologists with state-of-the-art medical technology. Patients from Kopar Khairane consistently rate us 4.8/5 Stars (based on 813 reviews) for our compassionate care, zero wait times, and instant report delivery.
The cost of a Angioplasty at our Kopar Khairane diagnostic center is highly competitive. We offer transparent pricing with zero hidden fees. Contact us directly for today's discounted rate.
For patients visiting from Kopar Khairane and across Navi Mumbai, Henotic Diagnostics guarantees fast turnaround times. Most Angioplasty reports are available the same day via secure WhatsApp delivery.
Yes! Our entire facility serving Kopar Khairane maintains strict NABL, ISO, and AERB accreditations to guarantee 100% precision for your Angioplasty.
Fill out the form below to secure your priority booking at our nearest center.
Loading booking form...




